Discover how appendicitis feels and its symptoms. Learn about the pain location, intensity, and other warning signs. Read on to understand the condition.
Continue readingSymptoms Of Internal Bleeding In Stomach: 5 Things You Must Know
Internal bleeding in the stomach, also known as gastrointestinal bleeding, is a potentially life-threatening condition that requires prompt medical attention. This type of bleeding can manifest in various ways, depending on the severity and location of the bleeding source.
Common signs and symptoms of internal bleeding include vomiting blood, which may appear as bright red or have a dark, coffee-ground-like consistency, and black, tarry stools resulting from partially digested blood. Other symptoms may include abdominal pain, weakness, dizziness, or fainting due to blood loss.
1. Symptoms Of Internal Bleeding In The Stomach
Recognising the symptoms of internal bleeding in the stomach is crucial for timely intervention and treatment. Here are some symptoms that may indicate blood flow disruption due to severe internal bleeding:
- Vomiting blood: Bright red or dark, coffee-ground-like in appearance
- Black, tarry stools: A result of partially digested blood
- Abdominal pain: Discomfort or cramping in the stomach region
- Weakness: Fatigue or general malaise
- Dizziness or fainting: Caused by blood loss and reduced blood flow to the brain
- Rapid heart rate: The body’s attempt to compensate for blood loss
- Pale skin and shortness of breath: Indicative of decreased blood volume and oxygen delivery
- Confusion and disorientation: Indicates enormous blood loss, which can lead to total loss of consciousness.
- Bruising: Bruising can occur around the navel, belly, and flank. Fractures can also lead to extensive bruising.
- Shortness of breath: This can be a symptom of internal bleeding in the stomach as the body struggles to compensate for the loss of blood volume, leading to reduced oxygen delivery to tissues and organs. This respiratory distress may be accompanied by feelings of weakness, dizziness, or even fainting.
2. Causes Of Internal Bleeding In The Stomach
Internal bleeding in the stomach can occur due to various conditions affecting the blood vessels and the lining of the gastrointestinal tract. The types of internal bleeding where this phenomenon occurs include:
Peptic Ulcers
Sores that develop on the stomach lining, oesophagus, or upper part of the small intestine, are often caused by Helicobacter pylori infection or nonsteroidal anti-inflammatory drugs (NSAIDs). Peptic ulcers can erode blood vessels, leading to internal bleeding.
Gastritis
Inflammation of the stomach lining may cause bleeding, resulting from factors such as excessive alcohol consumption, certain medications, infections, or autoimmune disorders.
Esophageal Varices
Swollen blood vessels in the oesophagus lining are commonly associated with liver disease. These fragile vessels can rupture due to increased blood pressure, leading to severe internal bleeding and requiring medical emergency.
Mallory-Weiss Tear
A tear in the lining of the oesophagus or stomach is typically caused by forceful vomiting or retching. This condition can damage blood vessels and cause internal bleeding.
Gastrointestinal Tumours
Benign or malignant growths in the stomach or intestinal lining can lead to bleeding as they invade blood vessels or disrupt the tissue.
Angiodysplasia
This condition involves the development of abnormal, fragile blood vessels in the gastrointestinal tract, which can rupture and cause internal bleeding.
Dieulafoy’s Lesion
A rare but potentially life-threatening cause of gastrointestinal bleeding, this condition involves the presence of an abnormally large artery in the stomach or intestinal wall that can rupture and bleed.
Hemorrhagic Gastritis
This acute form of gastritis is characterised by the rapid onset of bleeding from the stomach lining, often caused by severe stress, critical illness, or injury.
Aortoenteric Fistula
Aortoenteric fistula is a rare and life-threatening condition in which an abnormal connection forms between the aorta (the main artery in the body) and the gastrointestinal tract, resulting in massive internal bleeding.
Gastrointestinal Ischemia
Reduced blood flow to the digestive tract due to blocked or narrowed blood vessels can damage tissue and lead to internal bleeding.
Ingestion Of Caustic Substances
Accidental or intentional ingestion of corrosive chemicals or foreign objects can cause damage to the lining of the gastrointestinal tract, leading to internal bleeding.
Iatrogenic Injury
Internal bleeding in the stomach can occur due to medical procedures or treatments, such as endoscopy, surgery, or the use of certain medications that affect blood clotting.
Aneurysm
Internal bleeding may also be caused by an aneurysm, which represents a swelling in a blood vessel due to a weakened vessel wall. This weakness can lead to the rupture of the vessel. In some cases, an aneurysm rupture occurs during intense activity, while in others, it can happen unexpectedly during rest or sleep.
Aneurysms in the abdomen (abdominal aortic aneurysms) are common. If you suspect any of the symptoms mentioned above without relief, it’s best to seek immediate medical attention.
Blunt Force Trauma
Blunt force trauma is a significant cause of internal bleeding in the stomach, often resulting from high-impact events such as car accidents, falls, or physical assaults.
When the abdominal region experiences a forceful impact, the stomach’s blood vessels, organs, and tissues can be damaged, leading to internal bleeding.
In some cases, the bleeding may be slow and initially present without obvious symptoms, making it challenging to detect.
However, as enough blood accumulates within the abdominal cavity, individuals may experience discomfort, pain, and other signs of internal bleeding. Rapid detection and treatment are crucial in these situations, as severe internal bleeding can be life-threatening if left unaddressed.
Again, seeking medical attention and treatment is essential following a traumatic event with a potential abdominal injury, even without apparent symptoms.
Inflammatory Bowel Disease
Inflammatory Bowel Disease (IBD) encompasses chronic inflammatory conditions affecting the gastrointestinal tract, including Crohn’s disease and ulcerative colitis. These disorders can lead to internal bleeding in the stomach and other parts of the digestive system.
The inflammation associated with IBD can cause the mucosal lining of the gastrointestinal tract to become damaged and ulcerated.
As a result, blood vessels within the affected area may be compromised, and internal bleeding may occur.
The severity of bleeding can vary depending on the extent of the inflammation and the specific blood vessels involved.
Haemorrhoids
Haemorrhoids, although typically associated with the rectum and anus, can occasionally contribute to internal bleeding in the digestive tract, including the stomach.
These swollen blood vessels can develop around the anal region or within the rectum, leading to bleeding when irritated or strained.
3. When To See A Doctor For Internal Bleeding In Your Stomach?
While some cases of internal bleeding in the stomach may come with obvious symptoms, others might be more subtle, making it crucial to recognise the warning signs and seek medical help as needed.
Seek medical help if you experience common internal bleeding symptoms and symptoms of shock (due to rapid bleeding), such as:
- Rapid or weak pulse: The body tries to compensate for the blood loss by increasing the heart rate.
- Pale or cold, clammy skin: This results from decreased blood flow to the skin.
- Rapid, shallow breathing or shortness of breath: The body struggles to get enough oxygen due to reduced blood volume.
- Confusion or altered mental state: Decreased oxygen delivery to the brain may lead to cognitive impairments.
- Weakness or fatigue: The body cannot maintain normal energy levels due to blood loss.
- Low blood pressure (hypotension): Blood pressure drops as the body struggles to maintain adequate circulation.
- Decreased urine output: Reduced blood flow to the kidneys results in less urine production.
4. Treatment For Internal Bleeding In The Stomach
Addressing internal stomach bleeding is paramount to prevent severe complications such as organ failure and promote a full recovery.
A comprehensive treatment plan involves identifying the underlying cause, controlling the bleeding, and managing associated symptoms.
Stabilising The Patient
The first step in treating internal bleeding in the stomach is stabilising the patient. This may include administering intravenous fluids, blood transfusions, or medications to support blood pressure and prevent shock.
Diagnosis
Next, healthcare providers will use diagnostic tools, such as endoscopy, to identify the source of bleeding and determine the best course of action.
Endoscopy is often the first-line approach for diagnosing and treating internal bleeding in the stomach.
This procedure involves a flexible tube with a scope and specialised instruments to visualise the digestive tract, locate the bleeding site, and potentially treat the problem.
Endoscopic techniques can be used to cauterise, clip, or inject medications into blood vessel walls to stop the bleeding.
Surgery
In more severe cases or when endoscopic treatment is unsuccessful, surgery may be necessary to repair or remove the damaged tissue, blood vessels, or organs causing the bleeding.
Laparoscopic or open surgical techniques may be employed depending on the patient’s condition and the surgeon’s assessment.
Medication
Pharmacological interventions, such as acid-suppressing medications, may also be prescribed to facilitate healing and prevent further bleeding, especially in peptic ulcers or gastritis.
5. How To Prevent Internal Bleeding In The Stomach
Preventing internal bleeding in the stomach is an essential aspect of maintaining good gastrointestinal health.
Taking a proactive approach and following these strategies allows you to reduce the risk of developing stomach bleeding and associated complications.
Manage Underlying Medical Conditions
Keep chronic conditions, such as Inflammatory Bowel Disease, under control with regular follow-ups and treatment adherence.
Maintaining favourable blood pressure control and managing clotting factors in patients with bleeding disorders can also reduce the risk of internal bleeding.
Use Medications Responsibly
Be cautious with nonsteroidal anti-inflammatory drugs (NSAIDs) and blood-thinning medications, as prolonged use can increase the risk of stomach bleeding.
Always follow your healthcare provider’s recommendations and seek alternatives when appropriate.
Protect Your Stomach Lining
Adopt a healthy diet and limit the consumption of alcohol, caffeine, and spicy foods that can irritate the stomach lining.
Regular Check-Ups
Schedule routine physical examinations and screenings to detect and address potential issues early. Early detection and intervention can prevent complications related to internal bleeding in the stomach.
Avoid Risky Behaviours
Reduce your risk of trauma and injury by practising safe driving habits, wearing appropriate protective gear during sports, and maintaining a safe home environment to prevent falls.
Conclusion About Internal Bleeding In The Stomach
Addressing internal bleeding in the stomach is vital to prevent severe complications and promote optimal health. Understanding the warning signs, getting appropriate treatment, consulting with a professional colorectal specialist and following preventive measures can all significantly improve patient outcomes.
Always be proactive and vigilant in ensuring optimal gastrointestinal health.
Frequently Asked Questions About Symptoms Of Internal Bleeding In The Stomach
Can A Peptic Ulcer Cause Internal Bleeding?
Yes, a peptic ulcer can cause internal bleeding when the ulcer erodes the stomach or duodenal lining, damaging blood vessels.
How Can I Differentiate Between Stomach Cramps And Internal Bleeding?
Stomach cramps often cause intermittent pain and may be associated with certain foods, while internal bleeding typically presents with persistent pain, dark or bloody stools, and possibly weakness or dizziness.
How Long Can Internal Bleeding In The Stomach Go Unnoticed?
Internal bleeding in the stomach can go unnoticed for variable periods, depending on its severity; mild bleeding might be asymptomatic, while severe bleeding can cause rapid symptom onset.
Can Unexplained Weight Loss Be A Symptom Of Stomach Internal Bleeding?
Unexplained weight loss is not a direct symptom of internal stomach bleeding. Still, it may indirectly indicate an underlying issue, such as a peptic ulcer, which can cause internal bleeding.
What Does A Colorectal Doctor Do? A Comprehensive Guide
“What does a colorectal surgeon do?” is a question often asked by patients who need treatment for colorectal problems.
Colorectal surgeons are specialists in their field who treat, diagnose, and perform surgery on multiple conditions affecting the lower gastrointestinal tract. Also known as the GI tract, this part of the digestive system comprises the large intestine, colon, and anus.
Often, colorectal surgeons also work alongside gastroenterologists to treat conditions affecting the entire GI system. They may perform similar procedures and manage similar conditions.
When Should You Visit A Colorectal Surgeon?
A patient will typically consult a colorectal surgeon if they experience symptoms affecting their GI tract. Many patients start by seeing a general physician or gastroenterologist, who will later refer the patient to a colorectal doctor.
Medical conditions that will likely require treatment by a colorectal surgeon include:
- Inflammatory Bowel Disease (IBD)
- Colorectal cancer and polyposis
- Peritoneal carcinomatosis
- Hereditary nonpolyposis colorectal cancer (HNPCC)
- Anal cancer
- Appendix cancer
- Anal fistulas
- Hernias
- Rectal prolapse
- Perianal abscess
- Ischemia (blood supply loss)
- Gallstones
- Diverticular disease
- Ulcerative colitis
- Appendicitis
- Crohn’s disease
- Rectal bleeding
- Anal warts
- Haemorrhoids
- Constipation
- Rectal bleeding/gastrointestinal bleeding
Do Colorectal Surgeons Treat Conditions That Affect Only The Large Intestine?
While colon and rectal surgeons specialise in the large intestine, they also perform advanced general surgery.
Most of our body’s organs affect each other — this is why colorectal surgeons may often treat other organs closely linked with the large intestine or share the same conditions.
Other organs which a colorectal surgeon may treat include:
- Urinary tract
- Stomach
- Small intestine
What Qualifications Does A Colorectal Surgeon Have?
Board-certified colon and rectal surgeons will at least have completed a five-year training program in general surgery and additional training at an ACGME-accredited (Accreditation Council for Graduate Medical Education) colon and rectal surgery residency.
In addition to their proficiency in general surgery, colon and rectal surgeons also have specialised skills in performing endoscopies of the rectum and colon. They can also perform anorectal physiology techniques to examine and diagnose anal sphincter and pelvic floor disorders.
Many colorectal surgical residency programs offer training in minimally invasive surgery of the abdomen, including the rectum and colon.
What's The Difference Between A Colorectal Surgeon And A General Surgeon?
1. Specialty
The primary difference between a general and a colorectal surgeon is the level of depth and knowledge in treating specialised conditions.
General surgeons are typically trained in general GI tract surgery. Meanwhile, a colorectal surgeon has received in depth training in bowel surgery, especially in the colon and rectum.
2. Availability
General surgeons are available in many public hospitals and centres. While you can still find a colorectal surgeon in public health centres and communities, many opt for private practice.
3. Minimally Invasive Surgery
In urgent cases, a general surgeon is less likely to perform laparoscopic surgery than a colorectal doctor. The latter can comfortably perform minimally invasive surgery, especially for patients requiring emergency attention.
This is because they have a professional understanding and experience in advanced IBD principles and techniques, which a general surgeon does not have.
What Techniques Do Colorectal Surgeons Use?
Colorectal surgeons use various surgical and endoscopic techniques to treat their patients’ GI tracts. They have all the right equipment and tools to treat complex conditions, either through endoscopy, minimally invasive surgery, or open surgery.
Some techniques done by colorectal surgeons include:
- Colonoscopy – Examination of the digestive system (colon lining and rectum) to detect irregularities in the bowel and determine possible symptoms of colorectal cancer.
- Sigmoidoscopy – Diagnostic test for examining the sigmoid colon (lower part of the large intestine or colon), which is close to the anus and rectum. This may be done to get a tissue sample (biopsy) and diagnose symptoms such as diarrhoea, constipation, polyps, bleeding, abdominal pain, etc.
- Laparoscopic surgery – A minimally invasive surgery allowing a doctor to make small, 0.5 to 1.0 cm cuts on the patient to treat conditions that may develop inside the abdomen or pelvis.
- Gastroscopy– Non-surgical procedure to examine a person’s upper digestive system.
Aside from advanced surgery techniques, a colorectal surgeon can also perform different procedures, including:
- Endoscopic mucosal resection (EMR) or endoscopic submucosal dissection (ESD) – Removal of difficult tumours.
- Polypectomy – Surgical removal of polyps from the intestines.
- Bowel resection surgery – Removing the entire large bowel or parts of it. This surgery is also known as a colectomy.
- Ostomy surgery – An operation that redirects bowel contents to a stoma or an opening outside the abdomen connecting to the digestive system.
- Appendicectomy – Removal of an infected or inflamed abdomen.
- Anastomosis surgery – Reversal of an ostomy. This procedure reconnects the colon to the remainder of the rectum after most of it has been removed through colorectal cancer surgery.
- Rectopexy – Repair of rectal prolapse. It can be performed through an abdominal incision or keyhole surgery.
- Lateral internal sphincterotomy – Operation to treat an anal fissure or a tear in the anal opening which can cause itching, pain, and bleeding.
- Hernia repair – Surgical procedure for fixing a hernia (herniorrhaphy).
- Open and stapler haemorrhoidectomy – Excision of excess haemorrhoid tissue by lifting and returning it to its original position.
Conclusion On What Colorectal Surgeons Do
The domain of a colorectal surgeon lies in treating, diagnosing, and conducting surgery on medical conditions affecting the lower GI tract.
Although not all colorectal conditions need surgical treatment, visiting a colorectal specialist is advised, as they can treat your condition more effectively.
Dr Q.M. Leong is a colorectal surgeon in Singapore with decades of experience in his field. He specialises in treating haemorrhoids, gallbladder diseases, peptic ulcer, diverticular disease, and other GI diseases.
Need a colonoscopy screening? Book a consultation now or visit his colorectal clinic at:
Mount Alvernia Hospital
Medical Centre A
820 Thomson Road #01-06
Singapore 574623
Clinic Hours:
Monday to Friday, 8:30am – 12:30pm, 2pm – 5:00 pm
Saturday: 8:30am – 12:00pm
Sunday and Public Holidays: Closed
Frequently Asked Questions About
What Colorectal Surgeons Do
There are different instances where a general surgeon may refer you to a colorectal doctor. For example, you’ll need to visit a surgeon if they discover a large polyp in your stomach which can’t be removed through an endoscopy. The doctor may also refer you to a colorectal surgeon for a colon cancer diagnosis.
Colorectal surgeons can treat benign and malignant conditions and perform routine colon screening and surgery when needed. Meanwhile, a gastroenterologist is a doctor who has completed internal medicine training and gastroenterology.
It is possible to feel painful sensations that come and go away a few days after undergoing colorectal or bowel surgery. You may experience the following:
- Bowel cramps
- Tenderness due to incision
- Flu-like symptoms
- Low-grade fever
- Nausea
Depending on the procedures and techniques, many patients need to recover for several days in the hospital after colorectal surgery. They may need 3-6 weeks of recovery at home.
Yes. Contact a colorectal surgeon in Singapore if you experience irritable bowel syndrome symptoms such as:
- Bloating
- Constipation
- Diarrhoea
- Stomach cramps
- Frequent need for bowel movement
- Flatulence (excessive farting)
Anal Warts: Risks, Causes, Symptoms, and Prevention
Anal warts are a form of genital warts that appear inside or near the anus. Also known as condyloma cuminata, anal warts result from the Human Papilloma Virus (HPV). HPV is one of the most common sexually-transmitted diseases passed through direct contact. Warts first appear as small growths and may grow larger and occupy the entire anus.
Most cases of anal warts don’t result in any discomfort or painful sensations. Most patients won’t even know if they eventually develop these genital warts. But if the clumps grow much more prominently later on, they may lead to itchiness, bleeding, and a mucus discharge in some cases.
What Are The Causes Of Anal Warts?
Genital warts can look like small, flesh-coloured bumps that cover the part of the skin affected. They usually appear after a sexual encounter with an HPV-infected person. HPV may go away after some time for younger individuals and may not even lead to any visible signs and symptoms. However, the virus may stay longer in the body. It may also lead to the development of cancerous or non-cancerous genital warts.
A carrier transmits HPV through direct contact with the mouth, penis, vagina, or anus. However, sexual intercourse is unnecessary for the infection to spread. Individuals can pass HPV to another through direct skin-to-skin contact. Even if the warts are invisible or not yet formed, HPV contraction is still possible.
Who Are At Risk Of Anal Warts?
In general, men and women who have a sexually active lifestyle may get anal warts. A person increases their chances of spreading or contracting anal warts if:
- They’re consistently engaged in unprotected sex (not using any condoms or dental dams)
- They’re promiscuous or have multiple sexual partners all at once
- They frequently engage in anal/vaginal intercourse
- They’re sexually active at a young age
- They’ve had sexual relations with an HPV-carrier
- They have an immunocompromised immune system due to a chronic illness or medication
What Are The Symptoms Of Anal Warts?
Anal warts often begin as small bumps around the anal area and are no bigger than a pinhead. They’re usually too small to notice but can accumulate into large clumps over time. The clusters may match the colour of the surrounding skin tissue or maybe yellowish or pinkish.
Painful sensations or discomfort on the anus don’t usually accompany anal warts. Symptoms are rare, but there may be itchiness or a lumpy feeling around the anal region.
Other forms of genital warts can also appear simultaneously as anal warts. In women, the clusters may develop on the vagina, vulva, or cervix. Meanwhile, men can develop genital warts on the inside of their thighs, groin, scrotum, or penis.
If someone has engaged in oral sex with someone who has anal warts, this could also lead to a mouth infection. Warts may develop on the insides of the mouth or throat. Although benign, warts may make it difficult for the person to swallow or breathe properly due to partially blocked airways.
How Do Doctors Diagnose Anal Warts?
A doctor or colorectal specialist may diagnose anal warts by examining the anus. The patient will undergo an anoscopy. The doctor places a small tube to observe the lining of the anus and rectum. Through a visual inspection, they can determine the presence of anal warts.
If the patient isn’t responding to treatment well, the doctor may conduct a biopsy or request tissue samples. The reason is that HPV-infected individuals with anal warts are more prone to anal cancer.
What Is The Treatment For Anal Warts?
Treatment for anal warts can be invasive or non-invasive. A colorectal surgeon can surgically remove warts, or they can prescribe topical medications to the patient. In non-severe cases, warts go away on their own, and the individual may choose not to have them treated further.
Topical Medications
For small, non-cancerous anal warts, a doctor may recommend home treatment in the form of topical medication. Common medications for anal warts include podophyllin, trichloroacetic, and bichloroacetic acid. After applying the cream or gel, the patient may feel burning or discomfort for a few minutes. But they can resume daily activities immediately afterwards.
Some topical creams and gels may irritate the affected anal region. If you experience these, stop using the cream immediately and contact your colorectal physician.
Cryotherapy Or Burning
A doctor applies the liquid nitrogen to warts during cryotherapy to remove them. This procedure causes the tissues to freeze and eventually fall off.
Alternatively, the doctor may cauterise anal warts. Cauterising is done by “burning” the warts. The doctor will apply an acidic solution to destroy the tissue.
Surgery
If anal warts have become enlarged, the doctor can recommend a surgical procedure. The doctor will put the patient under general anaesthesia and then cut away the clumps using these instruments:
- Surgical blade
- Heated instrument
- Laser.
After surgery, the patient may need to take time away from work or school to recover. They may also need to return to the doctor for a few more rounds of surgery. This is the case if there are too many anal warts to remove in just one session.
How To Prevent Anal Warts?
Since the HPV virus stays in the body often without any warning signs, you can protect yourself from it (and anal warts) by taking these precautions:
- Get tested before and after engaging in sexual intercourse
- Avoid sexual contact with people who have anal or genital warts
- Always use protection when having sex
- Limit sexual contact to only one partner
- Get HPV vaccination to protect against this STD
Conclusion
Anal warts are a type of genital warts that form in the anus. An HPV-infected individual can pass warts onto others through direct skin contact.
In this guide, we’ve covered some basics about anal warts, including risk factors, prevention methods, symptoms, and causes. If you or someone you know has anal warts, it’s not a cause for concern as they go away over time. However, if you want to make sure you’re healthy, you can contact a trained colorectal surgeon in Singapore for treatment.
Dr Leong Quor Meng is a colorectal surgeon in Singapore specialising in colorectal cancers, hemorrhoids, anal fissures, hernias, and other related medical conditions. Get in touch with us now and tell us how we can help you.
Frequently Asked Questions About Anal Warts
A trained colorectal specialist can tell the difference between anal warts and haemorrhoids. Warts appear in clumps and feel rougher to the touch. Meanwhile, haemorrhoids, which are enlarged blood vessels, tend to be smoother.
If you can’t identify them yourself, it’s best to get in touch with a specialist who can examine and diagnose your colorectal condition.
No, anal warts aren’t usually painful. A person with anal warts can still do their day-to-day activities without being hampered.
Anal warts caused by HPV infections will go away after a few months or years. However, this doesn’t mean that the virus is no longer present in your body. As much as possible, get treatment for anal warts. Treatment prevents them from spreading and growing into larger and potentially painful clumps.
Endoscopy in Singapore – What It Is and Why It Is Done
If you’re dealing with ongoing stomach discomfort, reflux, bloating, or unexplained digestive symptoms, an endoscopy in Singapore is usually the next step. It helps your doctor look directly at what’s going on inside your digestive tract, instead of guessing based on symptoms alone.
Why You May Need an Endoscopy in Singapore
You may be advised to undergo an endoscopy procedure in Singapore if you have ongoing digestive symptoms that are not settling or are difficult to clearly explain based on the initial assessment.
In many cases, occasional stomach discomfort, nausea, or indigestion may not be serious on their own, but when symptoms persist or become more frequent, further evaluation is often recommended.
An endoscopy in Singapore allows a specialist to look directly at your upper or lower digestive tract to better understand what is causing your symptoms. It also helps doctors figure out whether further treatment or monitoring is needed.
Common reasons to consider an endoscopy include:
- Persistent abdominal pain or discomfort
- Rectal bleeding or blood in stool
- Ongoing reflux, heartburn, or indigestion
- Unexplained weight loss
- Abnormal blood test or imaging results
- Excessive bloating or changes in bowel habits
Beyond symptom evaluation, an endoscopy procedure in Singapore may also be used to:
- Identify the cause of digestive symptoms such as bleeding, pain, or bloating
- Assess the severity of existing gastrointestinal conditions
- Screen for conditions such as colorectal cancer or precancerous changes
- Take small tissue samples (biopsy) for further analysis
- Remove benign polyps if needed during the same procedure
- Monitor known or suspected gastrointestinal conditions
What Conditions Can Be Diagnosed with Endoscopy
With an endoscopy procedure in Singapore, a specialist can directly examine the digestive tract to identify a range of conditions that may be causing your symptoms. It also allows for targeted testing, including taking a small biopsy if something needs closer analysis.
Conditions that can be detected include:
- Inflammation of the oesophagus, stomach, or intestines (such as gastritis or oesophagitis)
- Stomach or duodenal ulcers
- Gastrointestinal infections, including bacteria such as H. pylori
- Polyps in the stomach or colon
- Gastroesophageal reflux disease (GERD)-related changes
- Sources of gastrointestinal bleeding (upper or lower tract)
- Signs of colorectal cancer or precancerous changes
- Coeliac-related or malabsorption-related changes in the intestinal lining
Types of Endoscopy Procedures Offered in Singapore
An endoscopy procedure in Singapore is not a single test for everyone. The type recommended depends on where your symptoms are coming from and what your doctor needs to investigate.
Upper Endoscopy (Gastroscopy)
A gastroscopy is used to examine the oesophagus, stomach, and upper part of the small intestine.
It is commonly recommended when you have symptoms such as:
- Persistent heartburn or reflux
- Stomach pain or discomfort
- Difficulty swallowing
- Unexplained nausea or vomiting
- Suspected ulcers or inflammation
- Unexplained weight loss
Lower Endoscopy (Colonoscopy)
A colonoscopy allows direct examination of the colon lining and can also include biopsy or removal of polyps during the same procedure if needed.
It is commonly used when there is:
- Rectal bleeding or blood in stool
- Changes in bowel habits (constipation or diarrhoea)
- Persistent abdominal pain or bloating
- Unexplained weight loss
- Suspicion of polyps or colorectal cancer
Sigmoidoscopy (Short Examination of Lower Colon)
A sigmoidoscopy is a shorter form of lower endoscopy that examines only the lower part of the large intestine (sigmoid colon). In some cases, it is used as an initial assessment before deciding if a full colonoscopy is necessary.
It may be recommended when:
- Symptoms are limited to the lower bowel
- A full colonoscopy is not immediately required
- There is rectal bleeding or suspected localised inflammation
- A quick evaluation of constipation or bowel changes is needed
Endoscopy Cost and Price in Singapore
The cost of an endoscopy in Singapore depends on what your doctor is investigating and whether any additional procedures are needed during the same session.
In general, the endoscopy price in Singapore is usually around SGD 800 to SGD 3,500+, depending on complexity and setting.
What Affects the Price of an Endoscopy in Singapore?
Several factors influence the final cost:
- Type of procedure (gastroscopy, colonoscopy, etc.)
- Whether biopsies are needed
- Sedation or anaesthesia required
- Specialist and facility fees
- Hospital or day surgery setting
Read on to learn more about factors affecting endoscopy prices in Singapore.
Can Medisave or Insurance Be Used for Endoscopy?
In many cases, Medisave and insurance can be used if the procedure is medically indicated. Coverage varies depending on your plan, and you can go through this with the clinic before the procedure, so there are no surprises.
What to Expect During an Endoscopy in Singapore
The procedure is straightforward, and most steps are planned to keep you comfortable and safe.
Before the Procedure
- You will usually be asked to fast for at least six hours before the endoscopy (or as instructed by your doctor)
- This ensures the stomach is empty for a clearer and safer examination
- If a colonoscopy is planned, a laxative may also be given to clear the bowels
- A local anaesthetic may be applied to reduce discomfort
- Sedation is given to help you stay relaxed and comfortable
During the Procedure
- A thin, flexible camera is gently inserted into the relevant part of your digestive tract
- The doctor examines the area in real time on a monitor
- The procedure typically takes around 15 to 30 minutes, depending on findings
After the Procedure (immediate monitoring)
- You will be observed for one to two hours until the sedation wears off
- In some cases, longer observation may be needed if treatment was done during the procedure
Recovery After an Endoscopy Procedure
After your endoscopy procedure in Singapore, you’ll be monitored until the sedation wears off. Most people go home the same day.
You might feel a bit bloated or drowsy, and if you had a gastroscopy, your throat may feel slightly sore. This usually settles within a day or two. You should be able to eat and return to normal activities fairly quickly, depending on how you feel.
Read on to find out more about what to expect during an endoscopy in Singapore.
Is Endoscopy Safe and Painful?
If you’re worried about an endoscopy in Singapore, that’s completely normal. Most patients feel anxious before the procedure, but endoscopy is generally safe and well-tolerated, especially with sedation used throughout.
Sedation helps keep you relaxed, and most patients do not feel pain during the procedure. Many also have little or no memory of it afterwards. The focus is always on making the experience as comfortable as possible while allowing accurate diagnosis.
After the procedure, it’s common to experience mild bloating, which usually settles fairly quickly. If you had a gastroscopy, you may also notice a slight sore throat. Most of these symptoms are temporary and typically resolve within 24 to 48 hours.
Risks and Complications
- Mild reaction to sedation
- Minor bleeding, especially if a biopsy is taken
- Infection (rare)
- Perforation in the digestive tract (very rare)
These risks are rare, and your endoscopy specialist will explain them before the procedure so you know what to expect.
Choosing an Endoscopy Specialist in Singapore
When you’re deciding on an endoscopy specialist in Singapore, it’s worth looking at more than just location.
What matters is:
- Experience in performing endoscopy procedures regularly
- Ability to interpret findings accurately
- Clear explanation of results and next steps
- Access to both diagnosis and treatment if needed
- Continuity of care if follow-up is required
Getting an Endoscopy in Singapore
If your symptoms have been lingering or affecting your daily life, an endoscopy in Singapore can give you clarity sooner rather than later.
At Advanced Colorectal and General Surgery Clinic, Dr Leong Quor Meng provides assessment and management for a wide range of digestive conditions, including endoscopy procedures. The first step is usually a consultation, where he’ll go through your symptoms and decide whether an endoscopy procedure in Singapore is appropriate for you, and what the next steps should be.
If you have persistent symptoms or need further evaluation, you can arrange a consultation for your condition.
Frequently Asked Questions About Getting An Endoscopy In Singapore
What factors affect the overall cost of an endoscopy in Singapore?
A few factors can impact the overall cost of an endoscopy, including the type of endoscopy being performed, the extent of the procedure, and the specific clinic or hospital in Singapore where it is done. Costs can also vary based on whether biopsies or other procedures are conducted during the endoscopy.
What is the average cost of an endoscopy?
In Singapore, the cost of an endoscopy can range from SGD 1,000 to SGD 3,000 or more. This range includes factors such as the type of endoscopy, the use of sedation, and any additional procedures or tests required.
How does the cost of an endoscopy in a private clinic compare to a public hospital?
Typically, the cost of an endoscopy in a private clinic is higher than in a public hospital. Private clinics often charge more due to shorter waiting times, more personalised care, and enhanced facilities. On the other hand, public hospitals in Singapore may offer lower prices due to government subsidies and larger-scale operations, but they might have more extended waiting periods for non-emergency procedures.
What are the costs of any necessary medications after an endoscopy?
The costs of necessary medications after an endoscopy can vary. Common medications might include pain relievers, antibiotics to prevent infection, or medications to manage conditions diagnosed during the procedure. These costs are usually not included in the initial procedure fee and can range from minimal to several hundred dollars.
How long does it typically take to receive results from an endoscopy?
Results from an endoscopy can be available immediately if the procedure is diagnostic, such as visualising the gastrointestinal tract. However, if biopsies or lab tests are conducted, it typically takes several days to a week to receive the results.
How does an endoscopy specialist handle complications during the procedure?
Endoscopy specialists in Singapore are trained to handle complications that may arise during the procedure. They closely monitor the patient’s vital signs and are prepared to manage issues such as bleeding, perforation, or adverse reactions to sedation. In the event of a complication, the specialist will immediately stabilise the patient and provide appropriate treatment.
Can an endoscopy specialist provide dietary and lifestyle advice post-procedure?
An endoscopy specialist in Singapore can provide dietary and lifestyle advice after the procedure. Based on the examination, the specialist may recommend changes to the patient’s diet, suggest lifestyle modifications, or prescribe medications to manage diagnosed conditions.
How often do endoscopy prices change in Singapore, and what influences these changes?
Endoscopy prices in Singapore can change periodically due to fluctuations in clinic operating costs, medical supply prices, and updates to healthcare regulations. Other factors such as advancements in endoscopy technology, changes in insurance coverage policies, and adjustments in government subsidies can also influence price changes.
What are the common factors that could lead to a higher price for an endoscopy in Singapore?
Several factors may result in higher cost of endoscopy in singapore, including the type of procedure (gastroscopy, colonoscopy, or specialised endoscopy), whether sedation is required, the reputation and experience of the doctor, and the facility where the procedure is performed (private vs public hospital). Additional diagnostic tests, biopsies, or polyp removal during the procedure can also increase the overall cost.
Are consultation fees included in the overall price of an endoscopy in Singapore?
In most cases, consultation fees are separate from the endoscopy procedure itself in Singapore. Typically, you’ll be required to pay for a pre-procedure consultation to assess your condition and a follow-up consultation to review the results. It’s important to check with your clinic to understand what is covered.
How does the complexity of the medical issue affect the endoscopy pricing in Singapore?
More complex medical conditions often require additional steps during an endoscopy, such as biopsies, polyp removal and the use of specialised equipment. This can increase the overall cost of the procedure. Complex cases may also necessitate a longer procedure time or the involvement of multiple specialists, further influencing pricing.
Ligation Of Hemorrhoids: 7 Things To Understand
Hemorrhoids is a common disease characterised by swollen blood vessels in the anus or lower rectum. Hemorrhoids can occur from straining during bowel movements or sitting for long periods on the toilet. All these can lead to increased pressure in the lower rectum, causing perianal swelling.
Different treatment options are available for hemorrhoids, such as over-the-counter creams and suppositories or tablets.
Another method is rubber band ligation of hemorrhoids. This option is available only for those suffering from internal hemorrhoids, and not external hemorrhoids.
1. What Is Ligation Of Hemorrhoids?
Rubber band ligation of hemorrhoids involves tying off the hemorrhoid at its base using a rubber band. This effectively restricts the blood flow to the hemorrhoid and causes it to fall off after 7 to 10 days.
As mentioned, rubber band ligation is only for the treatment of internal hemorrhoids, wherein the swollen blood vessels develop inside the rectum.
Symptoms don’t usually manifest for internal hemorrhoids, but painless bleeding during bowel movements is the most common symptom. Trace amounts of blood may appear on the toilet or tissue.
In such cases, the doctor may require hemorrhoid banding, especially when the patient reports other symptoms like prolapse.
2. Rubber Band Ligation Procedure For Hemorrhoids
To perform rubber band ligation, your doctor will insert an anoscope into your anal canal, allowing them to examine the hemorrhoid.
The doctor inserts a special instrument similar to a syringe but without the needle. It’s a safe and single-use device which sucksthe hemorrhoid tissue into the ligator.
The hemorrhoid is clasped with a small device to keep it in place. It will then wrap a rubber band around the hemorrhoid’s base, cutting off the blood flow and falling after several days.
Most rubber band ligation procedures occur in the endoscopy centre for about 5 minutes.. Patients may go home after the procedure and may continue with day-to-day activities.
3. Preparation For Hemorrhoid Banding
Before the hemorrhoid ligation, your doctor will provide pre- and post-procedure care instructions and teach you what to do.
Make sure you go over and follow them thoroughly on your own. This ensures a smooth-sailing procedure with minimal-to-no complications.
Consult with your doctor for any additional questions or concerns about the procedure. They’ll clarify everything with you beforehand for your peace of mind.
Due to the simplicity of hemorrhoid banding, you don’t need to undertake special preparations. You don’t have to fast or refrain from a high fibre diet to clear your bowels.
However, if you’re taking blood thinners, your doctor may advise you to stop taking them at least 7 days before the ligation or depending on the medication. This is to prevent excessive bleeding during the procedure.
Make sure to arrive on time for your scheduled appointment. You may have a friend or family member accompany you for added convenience.
4. What To Expect After Rubber Band Ligation?
Once the procedure is over, you may feel slight discomfort and fullness in your lower belly.
Some patients also report feeling like they need to take a bowel movement. All of these discomforts should go away several days post-operation. The doctor may prescribe pain medicine for added relief.
In the meantime, your doctor will ask you to refrain from doing any heavy lifting and sexual intercourse after the surgery. This is so you can make a full recovery and prevent other complications from arising.
5. Why Rubber Band Ligation Is Done
Rubber band ligation is a standard treatment for internal hemorrhoids. Patients who show symptoms even after several treatments may need to undergo surgery.
Rubber band ligation can’t be performed if not enough tissue is present for the ligator to pull.
Similarly, rubber band ligation may not be appropriate for third or fourth-degree hemorrhoids, wherein the hemorrhoid protrudes from the anus.
6. Effectiveness Of Rubber Band Ligation For Hemorrhoids
Hemorrhoid banding is a simple and safe procedure for treating first, second, and third degree hemorrhoids.
Further, the success rate for rubber band ligation ranges from 60% to 80%. Many patients who have undergone this procedure reported significant improvement in their overall quality of life.
7. Possible Complications After Rubber Band Ligation For Hemorrhoids
Here are some common post-treatment complications after rubber band ligation:
- Bleeding – There may be minor spotting when the hemorrhoid shrinks, which is normal and not a cause for concern. However, if you experience periodic bleeding, consult with your doctor for treatment.
- Urinary retention – You may have difficulty urinating after rubber band ligation. These complications usually begin within 24 hours after the procedure. Call your doctor, take some pain killers and be sure to monitor and make regular follow-ups regarding your condition.
- Infection in the anal region – Ligation of hemorrhoids rarely cause infection. Once again, call your doctor before trying out any at-home remedies.
Conclusion About Ligation Of Hemorrhoids
Hemorrhoid banding is a virtually pain-free surgery that removes internal hemorrhoids. The procedure takes 5 minutes to perform, allowing patients to go home on the same day.
For more information on hemorrhoid banding or hemorrhoids surgery in Singapore, contact Dr Leong Quor Meng and set an appointment today.
He is a colorectal surgeon in Singapore specialising in treating hemorrhoids, gallbladder, peptic ulcer, gastritis, hernia, anal fistulas, abscesses, diverticulitis, and other changes in bowel habits.
Frequently Asked Questions About Ligation of Hemorrhoids
No, banding is relatively painless. But often patients experience some discomfort and feel they need to pass motion after banding. This sensation should improve after 24 hours.
The recovery time for hemorrhoid banding will depend on the patient and the number of hemorrhoids for ligation. But it takes one to two weeks on average before the tissue fully heals. You may speed up the recovery process by refraining from strenuous activities like
- Weight lifting
- Aerobic exercises
- Jogging
- Biking
After the procedure, you may feel the urge to take a bowel movement. However, you’re strongly advised not to empty your bowels to prevent loosening the band off the hemorrhoid.
Hemorrhoid ligation is the most effective treatment for internal hemorrhoids. When done by an experienced colorectal surgeon, you can expect a low recurrence rate of 25%.
No. Haemorrhoid ligation is normally done immediately after a colonoscopy and hence you will still be asleep while the ligation is being done.
A Detailed Guide To Colorectal And General Health Conditions
In our current day and age, there are numerous health factors vying for our constant attention. From cardiovascular conditions to hypertension and diabetes, along with managing chronic stress levels, it’s easy to only focus on conditions which have a more tangible and immediate impact on our health. However, one area that often remains neglected is colorectal health, due to it playing an essential yet understated role as compared to other organs in the body.
The colon plays an important role in digestion, helping to absorb water and store food waste while utilising muscle contractions to move waste to the rectum to be expelled from the body. The colon has a smooth inner lining consisting of millions of cells, and changes in these cells can lead to conditions that many Singaporeans face, such as colorectal cancer, piles, and diverticular disease, amongst others.
Beyond colorectal conditions, other conditions such as gallstones, hernias, and abscesses can significantly affect one’s quality of life. While some conditions are merely unsightly or cause mild discomfort, others can be potentially life threatening if unaddressed due to the risk of complications, requiring surgery to treat them.
The saying of ‘prevention is better than cure’ certainly applies to various colorectal and health conditions. Compared to other types of cancer, colorectal cancer has a much higher rate of recovery if detected and treated early, with up to 90% of cases being fully cured if discovered in time. This highlights the importance of visiting a professional colorectal surgeon in Singapore to arrange for regular screening and treatment if necessary.
With over 10000 successful procedures, Dr Leong is an experienced endoscopist and surgeon who specialises in Single Incision Laparoscopic (keyhole) Surgery, as well as minimally invasive General Surgery. He also provides same day colonoscopy services at his Singapore-based clinic, in addition to treating a variety of colorectal conditions, making it a smooth and comfortable affair when seeking treatment or screening tests.
Read on to learn more about various colorectal and general conditions, their symptoms and risk factors, as well as the available treatment methods.
Part 2: Key Colorectal Conditions
In this section, we will cover a few major colorectal conditions, such as colorectal cancer, piles, and diverticular disease.
2.1 Colorectal Cancer
Colorectal cancer refers to cancer that occurs in the colon (large intestine) or rectum area. It usually starts from benign polyps, which are fleshy clumps of tissue that form on the inner lining of the colon or rectum. If left untreated, these polyps can develop into malignant tumours across a duration of 5 to 10 years, spreading to nearby organs or lymph nodes. When this happens, it is known as metastasis, making colorectal cancer much harder to treat as well as being life-threatening.
Statistics have shown that colorectal cancer is the most common cancer in Singaporean males, while being the 2nd most common cancer in Singaporean females. Colorectal cancer tends to not exhibit any outward symptoms at the early stages. At later stages, common symptoms include a change in bowel habits such as diarrhoea or constipation; the presence of blood in your stools, as well as persistent abdominal discomfort such as cramps, flatulence, or pain. It is essential to visit a colorectal clinic in Singapore if you experience any of these symptoms.
Some risk factors of developing colorectal cancer are as follows:
- Having a family history of colorectal cancer
- Being over 50 years of age
- Smoking and heavy alcohol use
- A diet high in red and processed meats
- Being overweight
- An inactive lifestyle
One of the greatest dangers of colorectal cancer is that it usually does not present symptoms until it is at an advanced stage, which may greatly complicate treatment and significantly lower the likelihood of a complete recovery. The good news is that regular screening is highly effective at detecting colorectal cancer in Singaporeans, allowing for early and effective treatment at the initial stages. Screening comprises a variety of tests, such as fecal immunochemical tests, double-contrast barium enema, as well as colonoscopies.
A colonoscopy is a procedure where a colonoscope, which is a 1.6m flexible tube with a video camera at the end, is inserted into the rectal region to allow for visual examination of the entire colon lining. Colonoscopy clinics in Singapore are well-versed in conducting colonoscopies, with the entire procedure taking about 20 to 30 minutes from start to end. It is conducted with general anaesthesia, making it a painless affair. In addition, a colonoscopy can identify and remove benign polyps, making it both a diagnostic and therapeutic procedure. An estimated 90% of polyps can be removed during colonoscopy, preventing the need for further surgery.
Prior to a colonoscopy, your doctor will inform you on what you should eat and how to empty your bowels for a smooth procedure. Dr Leong is a firm believer of Same Day Colonoscopy, where the consult, bowel preparation, colonoscopy, and results of the procedure all occur on the same day. With colonoscopies only being required approximately every 10 years, a reputable colonoscopy clinic in Singapore plays an important part in promoting screening and prevention of colorectal cancer by making the process smooth and comfortable.
Similar to other cancers, colorectal cancer is diagnosed across Stages 1 to 4. Generally, Stages 1 and 2 require surgery alone, while Stages 3 and 4 require surgery in combination with chemotherapy and/or radiotherapy/immunotherapy. Treatments vary from patient to patient, with doctors factoring in the stage of cancer when diagnosed as well as the overall health of the patient.
Contact our colorectal clinic in Singapore today to find out more about our screening and treatment procedures.
2.2 Piles
Piles, also known as haemorrhoids, are swellings containing enlarged blood vessels, and can be found either inside or around the rectum or anus. They are caused by increased pressure in the blood vessels in and around your anus, which can cause these vessels to become swollen and inflamed, resulting in discomfort and bleeding. In severe cases, it is advised to seek treatment for piles in Singapore.
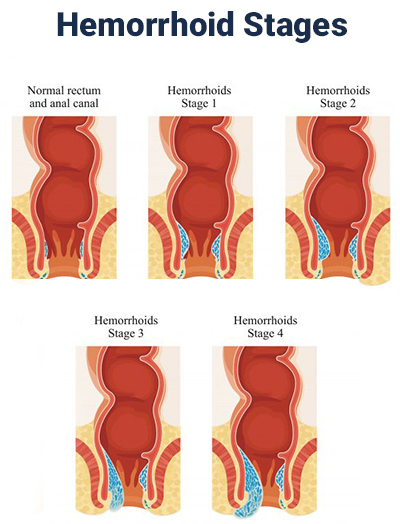
Haemorrhoids can be classified based on four degrees based on size and severity.
- First degree: small swellings that develop on the inside lining of the anus and remain inside
- Second degree: larger swellings that prolapse (appear) when defecating, before spontaneously reducing (going back inside)
- Third degree: swellings that prolapse during defecation, but require digital reduction (with a finger)
- Fourth degree: swellings that are persistently prolapsed
Often, most people do not realise they have haemorrhoids until they exhibit symptoms, such as:
- Bleeding after passing a stool (with bright red blood)
- An itchy sensation at the anus
- A lump that hangs down outside the anus
- Mucus discharge after passing a stool
- Soreness, redness, or swelling around the anus
One of the main risk factors that can increase the likelihood of haemorrhoids is spending too much time seated on the toilet, causing blood vessels around the anus to be congested and enlarged. Other risk factors include having a family history of haemorrhoids, weakening of your body’s supporting tissues with age, as well as increased pressure on pelvic blood vessels as a result of pregnancy.
Generally, treatment for piles in Singapore varies based on the aforementioned degree of severity. For First and Second degree haemorrhoids, topical medication and lifestyle changes are often sufficient. Some lifestyle changes include increasing the amount of fibre in your diet via fruits and vegetables, drinking plenty of water, avoiding constipation medicine, and exercising regularly to reduce both weight and blood pressure.
One non-surgical procedure is rubber band ligation, where a tight elastic band is wound around the base of the haemorrhoid, cutting off its blood supply and letting it fall off naturally after a week. Other non-surgical procedures include injecting a chemical solution into haemorrhoid tissue to shrink it, or using coagulation techniques involving infrared light or heat to harden and shrivel haemorrhoids.
For Third and Fourth degree haemorrhoids, your doctor will likely recommend you to undergo surgery. Before undergoing surgery treatment for piles in Singapore, your surgeon will inform you of the risks that may occur after haemorrhoid surgery, ranging from bleeding, infection, urinary retention, faecal incontinence, and stenosis. Two options include undergoing a haemorrhoidectomy or a stapler haemorrhoidopexy.
A haemorrhoidectomy is the most effective and complete way of treating severe or recurring haemorrhoids, where small cuts are made around the anus to slice them away. It is conducted with either general or local anesthesia to reduce the pain, and takes a couple of weeks for recovery. A stapled haemorrhoidopexy is used to treat prolapsed haemorrhoids and is also carried out under anaesthesia, which uses stapling to block blood flow to haemorrhoidal tissue and causing them to shrivel up.
2.3 Diverticular Disease & Diverticulitis
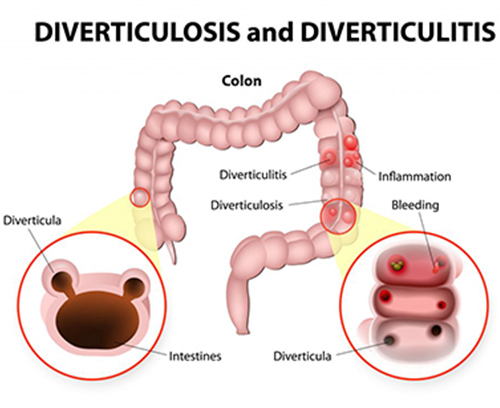
Diverticular disease stems from diverticula, which are small bulges or weakness that develop in the lining of the colon as Singaporeans age. They are formed by increased pressure on weakened spots along the intestinal walls, such as experiencing straining during constipated bowel movement. Generally, diverticula are discovered during a routine colonoscopy or CT scan, or if patients are exhibiting symptoms of discomfort.
There are three varying diagnoses related to diverticula. If diverticula are present but exhibiting no symptoms, it is known as diverticulosis. Diverticulosis is very common and affects approximately 50% of people over 60 years of age, but generally results in no negative symptoms. Diverticular disease occurs when symptoms are exhibited, and diverticulitis is when infection or inflammation occurs as a result of diverticula tearing.
Some symptoms of diverticular disease in Singaporeans include abdominal pain that is aggravated by eating and relieved by bowel movement or flatulence, constipation or diarrhoea, as well as occasional blood in stools. With diverticulitis, additional symptoms include constant and more severe abdominal pain, along with the onset of a fever.
Here are some of the risk factors that can increase the risk of diverticulitis:
- Aging
- Obesity
- Smoking
- Lack of exercise
- A low-fibre and high fat diet
- Certain medications
If left untreated, diverticulitis can result in complications such as abscesses, stenosis, fistulas, and peritonitis. Peritonitis in particular is a medical emergency due to the rupturing of the infected diverticula and spilling intestinal contents into your abdominal cavity. Treatment for Singaporeans experiencing diverticular disease and diverticulitis depends on the severity of complications.
For mild cases, a high fibre diet with painkillers and antibiotics may be sufficient, as well as adopting lifestyle changes such as a healthier diet and increased exercise. Severe cases usually require a colectomy, which is the removal of the affected section of your large intestine and helps treat fistulas, peritonitis, and stenosis. To facilitate surgery, most surgeons utilise a technique known as percutaneous drainage to first deal with abscesses. A needle or catheter is inserted through the skin into the abscess to drain the infected fluid, facilitating an easier surgery process for diverticulitis.
Part 3: General Health & Surgery
Beyond colorectal conditions, there are other conditions that can affect one’s quality of life. Learn more about their symptoms and risk factors, as well as how surgery is effective in treating them.
3.1 Gallstones & Gallbladder Surgery
Gallstones, also known as gallbladder stones, are hardened deposits that form in your gallbladder. Bile is a liquid produced by your liver to help digest fats, and is passed into the gallbladder via bile ducts. Doctors suggest that high levels of cholesterol and bilirubin in your bile contribute to the formation of gallstones. Gallstone surgery is often required for Singaporeans who exhibit severe symptoms that impact their quality of life.
Some risk factors for developing gallstones include:
- Being over 40 years of age
- Being female
- Having a family history of gallstones
- Eating a high fat/cholesterol diet
- Being overweight
- Lack of exercise
Gallstones are a common occurrence, affecting an estimated 1 in every 10 adults. Generally, gallstones do not exhibit symptoms unless they become trapped in an opening inside your gallbladder. In such scenarios, blocked gallstones can cause a sudden and intense abdominal pain known as biliary colic. Left untreated, gallstones can lead to other complications such as jaundice (yellow skin), cholecystitis (inflamed gallbladder), and pancreatitis as a result of a blocked pancreatic duct, which can be life-threatening.
Gallstone surgery in Singapore is often required if complications to one’s health arise. A surgeon will conduct a laparoscopic cholecystectomy, also known as keyhole surgery, for symptomatic cases. A surgeon will make 4 small incisions in your abdomen, before a laparoscope is inserted to help identify and remove the gallstones. Imaging tests may be utilised as well to identify other related problems in your bile duct. As an established medical procedure that takes approximately 1 to 2 hours, keyhole surgery is usually a smooth affair for patients.
Dr Leong specialises in conducting Single Incision Laparoscopic Surgery (SILS). SILS confers a number of advantages over traditional keyhole surgery, such as significantly reduced pain and lowered risk of infection due to only requiring a single incision, helping to expedite patients’ recovery. It also provides a more cosmetic option by leaving no scar, due to the insertion of instruments through the navel region.
Prior to a surgery, your doctor will inform you on preparations you need to take, such as avoiding food and drink the night before surgery as well as stopping certain medications and supplements to minimise bleeding. Contact our colorectal clinic in Singapore today to learn more about SILS and how we treat gallstones.
3.2 Hernias
A hernia occurs when an internal organ or body part protrudes through the wall of muscle or tissue that normally contains it. It usually shows up as a lump that may go away when it is pressed or when you lie down. They can cause pain when coughing, bending over, or lifting heavy objects, and treating hernias requires professional help from surgeons in Singapore.
Hernias arise as a result of muscle weakness and strain, and can either develop quickly or over a long duration of time. Some risk factors include being overweight, doing strenuous exercise, undergoing a pregnancy, experiencing chronic coughing or constipation, as well as ageing.
Here are some of the most common types of hernia:
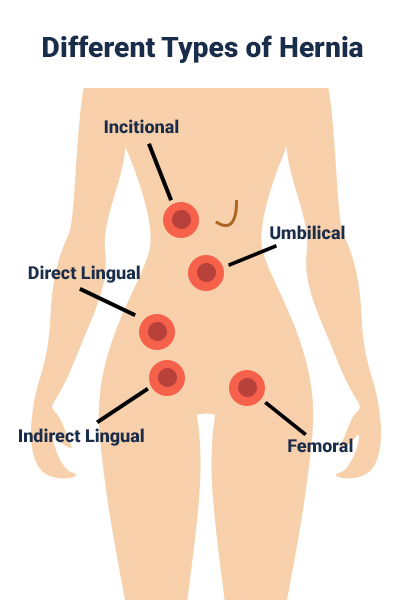
- Inguinal hernias occur when fatty tissue or a part of the intestine protrudes into the groin at the top of the inner thigh. It mainly affects men, and is associated with ageing and repeated strain on the tummy. Inguinal hernias can be further classified into direct and indirect inguinal hernias, with the latter having a higher risk of bowel complications
- Femoral hernias also occur when fatty tissue or part of the intestine protrudes into the groin at the top of the inner thigh. They occur less frequently and tend to affect older women. They carry a high risk of bowel complications and should be addressed with surgery.
- Umbilical hernias occur when fatty tissue or part of the intestine protrudes through the abdomen near your belly button. It can occur due to previous incisions such as keyhole surgery, or due to obesity. They are common in newborns and infants, and can also affect adults as well.
In particular, complications of inguinal and femoral hernias can result in obstruction and strangulation. Obstruction occurs when part of the intestine becomes stuck in the inguinal canal, causing stomach pain and vomiting. Strangulation occurs when part of the intestine becomes trapped and cuts off blood supply, necessitating emergency surgery to prevent tissue death.
Similar to treating gallstones, hernia surgeons in Singapore can either utilise open or laparoscopic (keyhole) surgery to treat hernias. Open hernia surgeries involve an incision into the groin, before the surgeon pushes the hernia back into the abdomen before strengthening the abdominal wall with stitches or synthetic mesh. Keyhole surgeries utilise a laparoscope to allow for a smaller incision, promoting faster recovery and less pain but require the expertise of a trained surgeon.
3.3 Cyst & Abscess Removal
Cysts and abscesses occur throughout the body and are a common occurrence that affect numerous Singaporeans. In certain circumstances, surgical removal is highly recommended to improve one’s quality of life and prevent further infection and inflammation.
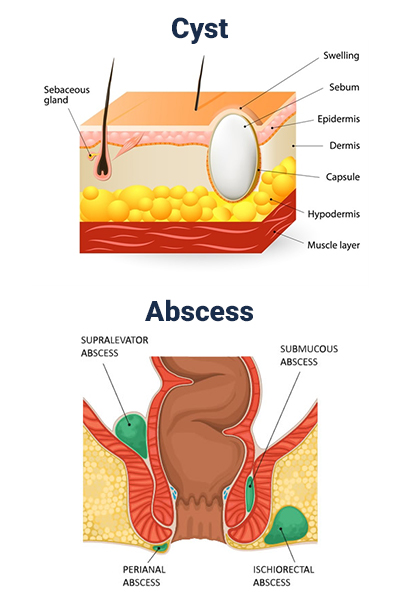
A cyst is a sac that is filled with fluid, air, or other material, and is generally harmless. A sebaceous cyst is a lump under the skin filled with sebum, which is an oily and waxy protective substance produced by your sebaceous glands. They may become infected due to bacteria growth, leading to enlargement and pain which may require surgery to treat if antibiotics and anti-inflammatory drugs fail to improve its condition.
An abscess is a collection of pus that has built up within the tissue. A perianal abscess is one of the most common types of abscesses, appearing as a painful swelling near the anus. Left untreated, anal abscesses can result in a complication known as an anal fistula, which is a small tunnel that forms between the abscess and an opening on the skin around the anus. It allows faeces to collect, resulting in chronic infection with pus and discharge.
Cyst formation is caused by a variety of reasons, ranging from genetic conditions to cell defects, chronic inflammatory conditions, blocking of ducts which cause fluid buildup, or injuries. Some factors that can increase the likelihood of abscess formation are a weakened immune system, as well as having other conditions such as diabetes, Crohn’s disease, or being overweight.
One of the main techniques utilised for cyst and abscess removal in Singapore is drainage. A small incision is made to insert a needle, facilitating the drainage of liquid (for cysts) or pus (for abscesses) before the wound is packed with gauze. It is a simple procedure that allows for local anaesthesia, as well as a speedy recovery.
There are multiple surgery procedures to treat anal fistulas, depending on the nature of the fistula, as well as aiming to avoid damage to the sphincter muscles that can lead to bowel incontinence. A fistulotomy is the most common and effective treatment for anal fistulas, cutting open the whole length of the fistula to allow it to heal into a flat scar. For more complex fistulas, other surgery procedures include inserting a seton, an advanced flap procedure, as well as a LIFT procedure.
Part 4: Conclusion
With the numerous conditions that can affect one’s colorectal health, it is important to learn about their symptoms and risk factors, allowing you to recognise them and promptly visit your doctor for effective treatment. In addition, undergoing regular colorectal cancer screening in Singapore is essential in avoiding an easily preventable condition, giving you the peace of mind to enjoy life with your loved ones.
Contact our colorectal clinic in Singapore today and take the first step into a better and healthier tomorrow.
Can Crohn’s Disease Kill You? Understand The Risks
Characterised by chronic inflammation in the gastrointestinal (GI) tract, Crohn’s Disease is an (IBD) that affects millions of individuals worldwide and poses unique challenges.
The question is, can Crohn’s Disease kill you? The short answer is no. The disease itself is not fatal, but certain complications can be life-threatening.
This article explores Crohn’s Disease in-depth, shedding light on what it is, potential causes, and the often subtle signs that may signal its presence. We’ll also tackle several factors that impact life expectancy for those affected by this chronic condition.
What Is Crohn’s Disease?
Crohn’s Disease is a medical condition characterised by long-lasting and chronic inflammation in the gastrointestinal (GI) tract. This inflammation can occur in different parts of the digestive system, including the mouth, anus, and other area.
The symptoms of Crohn’s Disease may vary in intensity from one individual to another, depending on the severity of inflammation.
Risk Factors Of Crohn’s Disease
Despite extensive research, the exact cause of Crohn’s Disease remains elusive. However, there are several recognised factors that contribute to its development, including genetic predisposition, environmental influences, and an abnormal immune response.
- Genetic Predisposition: Individuals who have family members or relatives with this disease are at higher risk. If one parent has Crohn’s disease, the risk for their child to develop the condition is estimated to be around 7-9%. If both parents have it, the risk goes up to 35% or more.
- Environmental Factors: Dietary choices, smoking, and exposure to infections may contribute to the development or exacerbation of Crohn’s Disease in susceptible individuals. For example, diets high in fat or refined foods and low in fibre can affect the composition and function of the gut microbiota, potentially leading to increased gut inflammation, and influencing the severity and frequency of flare-ups.
- Abnormal Immune Response: An overactive immune system can mistakenly target the GI tract, triggering chronic inflammation. The resulting inflammation damages the intestinal walls and can lead to various symptoms associated with Crohn’s disease.
- Age and Gender: Crohn’s Disease is most commonly diagnosed in people between 15 and 35 years old. It affects both men and women, although some research suggests that it may be more prevalent in females.
- Ethnicity: While Crohn’s Disease occurs in people of all ethnic backgrounds, it is more common in individuals of Ashkenazi Jewish descent and historically in North America and Europe. Recent trends show increasing cases in African, Hispanic, and Asian populations, possibly due to changes in lifestyle and environment.
Common Symptoms Of Crohn’s Disease To Look Out For
The thing about the symptoms of this inflammatory bowel disease is that they develop gradually, making them easy to dismiss or attribute to other diseases.
However, it’s essential to pay attention to these symptoms, especially if you have one or more of the above-mentioned risk factors as left unchecked; they can worsen over time. Here are some sneaky signs of Crohn’s Disease to be aware of:
Persistent Abdominal Pain
Chronic or recurrent pain in the abdomen is one of the signs of IBD. This pain can range from mild discomfort to severe cramping and may be mistaken for indigestion or other gastrointestinal issues.
Unlike normal indigestion where the pain is usually felt in the upper abdomen and is more generalised, abdominal pain associated with Crohn’s disease often occurs in the lower right side of the abdomen. However, it can also affect various areas within the GI tract.
Diarrhoea And Blood In Stool
Diarrhoea from Crohn’s disease is chronic and can be severe, leading to dehydration and nutrient deficiencies. It is usually accompanied by abdominal pain and may contain blood or mucus due to the inflammation and ulceration of the intestinal walls. This differs from typical diarrhoea, which might be acute, related to an infection or dietary indiscretion, and resolves in a few days.
Meanwhile, rectal bleeding in Crohn’s disease is usually a sign of inflammation or ulceration in the colon or rectum. It can range from small amounts of blood on the toilet paper to significant bleeding evident in the stool.
The bleeding is persistent and often accompanied by other symptoms of Crohn’s disease. In contrast, normal rectal bleeding, such as that from haemorrhoids or minor anal fissures, might be occasional and not associated with chronic intestinal inflammation.
Unexplained Weight Loss
Many individuals with Crohn’s Disease experience unexplained weight loss, even when they haven’t intentionally changed their diet or exercise habits. This is often due to malabsorption of nutrients in the inflamed digestive tract and reduced appetite.
While intentional weight loss typically results in a healthier and more controlled change in physique, weight loss due to Crohn’s disease is often rapid, unintended, and associated with signs of malnutrition and illness, leading to a more unwell appearance.
Fatigue And Weakness
Chronic inflammation associated with Crohn’s Disease can lead to fatigue and weakness, which may be attributed to stress or lack of sleep. Patients with this condition have low energy and often feel their exhaustion is never-ending and not going away despite rest.
Extraintestinal Symptoms
Crohn’s Disease doesn’t only affect the digestive tract; it can also have extraintestinal manifestations that affect other parts of the body. These can include:
- Joint Pain: Arthritis or joint pain, especially in the knees, wrists, or ankles, can occur in individuals with Crohn’s Disease.
- Skin Problems: Skin conditions like rashes, ulcers, or erythema nodosum (painful red nodules) can be related to Crohn’s Disease.
- Eye Inflammation: Inflammation of the eyes, known as uveitis, can occur in people with Crohn’s Disease, causing redness, pain, and vision problems.
Factors That Can Affect Lifespan For Patients With Crohn’s Disease
While Crohn’s Disease presents challenges, it is not a death sentence, and many individuals with the condition lead long, fulfilling lives. In fact, a 2022 study in Sweden shows that the net survival of people with Crohn’s Disease has improved significantly compared to past decades.
It was 54% for those diagnosed between 1963–1985, 88% for those diagnosed between 1986–1999, and up to 93% for individuals diagnosed between 2000–2010.
However, several factors can influence how long you can live with Crohn’s Disease. These are:
Disease Severity
The extent and severity of inflammation in the digestive tract play a crucial role in determining how long you can live with Crohn’s Disease. Mild to moderate cases of Crohn’s Disease, or cases with less aggressive to more persistent symptoms, generally have a better long-term prognosis than severe cases.
This is due to the increased risk of serious complications like bowel obstruction, malnutrition, and systemic inflammation affecting other organs. Additionally, the persistent severe inflammation and the need for aggressive treatments can lead to secondary conditions, such as infections or cardiovascular disease, further impacting overall health and longevity.
Timely diagnosis and effective management can help prevent the progression of the disease to a more severe state.
Body’s Response To Treatment
The variability in how individuals respond to treatments for Crohn’s Disease can profoundly impact their long-term health outcomes and lifespan. Patients who respond well to treatment may experience prolonged periods of remission, fewer complications, and a better quality of life, contributing to a longer lifespan.
On the other hand, patients with a poor response to treatment may suffer from persistent, active disease and frequent flare-ups, leading to ongoing inflammation, more severe intestinal damage, and a higher risk of serious complications like strictures, fistulas, or even colorectal cancer.
These complications can mean more aggressive treatments, which could carry their own risks and can further impact overall health and lifespan.
Complications
It’s important to note that Crohn’s Disease can still lead to complications, particularly if left untreated or poorly managed. Here are some of the complications that have a significant impact on an individual’s lifespan.
- Malnutrition: Chronic inflammation in the digestive tract can lead to malabsorption of essential nutrients. Malnutrition can result in weight loss, weakness, and vitamin deficiencies, which can affect overall health and vitality.
- Infections: Individuals with Crohn’s Disease may have a higher risk of developing infections, particularly if they are taking immunosuppressive medications to manage their condition. Serious infections, such as Tuberculosis (TB) and Septicemia, can be life-threatening if not treated promptly.
- Bowel Obstruction: The inflammation and scarring associated with Crohn’s Disease can lead to bowel obstructions. These blockages can cause severe pain, vomiting, and dehydration. In some cases, emergency surgery, such as open and laparoscopic surgery, may be necessary to relieve the obstruction.
- Fistulas: Crohn’s Disease can cause abnormal connections (fistulas) to form between different parts of the digestive tract and between the digestive tract and other organs. Fistulas can lead to complications such as abscesses and sepsis if not managed effectively through Biologic Therapies or Fistulotomy.
- Cancer: Individuals with long-standing Crohn’s Disease have a slightly higher risk of developing colorectal cancer. Regular surveillance and colonoscopies are recommended to detect any precancerous changes or malignancies at an early and treatable stage.
Age And Gender
In a study by published in the Canadian Medical Association Journal, it was found that the death age for people with Crohn’s Disease and other inflammatory bowel diseases is 78.5 for males and 78.4 years for females.
Sadly, the life expectancy of a child with Crohn’s Disease is shorter. Researchers at Sweden’s Karolinska Institutet reveal that children who develop inflammatory bowel diseases below 18 years of age are at higher risk of mortality both during childhood and into adulthood. They have a mortality rate of three to five times higher than those without IBD.
Crohn’s Disease Diagnosis

Early detection is paramount in effectively managing Crohn’s Disease, as it allows for timely intervention to control inflammation, prevent complications, and improve the patient’s quality of life. A prompt diagnosis can also positively impact life expectancy.
To confirm the presence of Crohn’s Disease, healthcare providers utilise a combination of medical history assessments, physical examinations, and various diagnostic tests.
- Medical History: In the diagnostic process, medical history serves as a foundation, enabling healthcare professionals to gain insights into the patient’s symptoms, family history, and risk factors.
- Physical examinations: These tests provide additional information, including signs of abdominal tenderness, swelling, or other physical manifestations of the Disease.
- Endoscopy: This involves procedures like a colonoscopy and an upper endoscopy, allowing for direct visualisation of the gastrointestinal tract. Biopsies can be taken during these tests to confirm inflammation characteristic of Crohn’s Disease.
- Imaging: Magnetic Resonance Imaging (MRI) and Computed Tomography Scans (CT scans) provide detailed images of the digestive tract, helping identify affected areas and evaluate the extent of inflammation.
- Blood Tests: Blood tests are essential because they can reveal signs of inflammation, anaemia, or nutritional deficiencies often associated with Crohn’s Disease.
- Stool Tests: Analysing stool samples can help identify infections or other conditions that may mimic Crohn’s Disease symptoms.
- Biomarker Testing: Certain biomarkers, such as C-reactive protein (CRP) and faecal calprotectin, can be measured to assess disease activity and response to treatment.
A definitive diagnosis of Crohn’s Disease is typically based on a combination of these assessments, enabling healthcare providers to tailor treatment plans to the individual’s specific needs.
Crohn’s Disease Pain Management

While Crohn’s Disease can impact one’s health and quality of life, significant advances in medical research and treatment options have substantially improved the lives of many individuals with Crohn’s disease.
Pain management strategies often involve a multi-faceted approach, considering both medication and lifestyle modifications.
- Acetaminophen (Tylenol): Acetaminophen is often prescribed for pain relief as it does not typically exacerbate inflammation in the gastrointestinal tract. However, it may not be as effective for severe pain.
- Antispasmodic Medications: Antispasmodic drugs like dicyclomine or hyoscyamine can help relieve abdominal cramping and spasms.
- Opioid Medications: Opioids, like codeine or tramadol, may be prescribed for severe pain in Crohn’s Disease for short-term use.
- Corticosteroids: Corticosteroids, such as prednisone, may be used during disease flares to reduce inflammation and alleviate symptoms, including pain. They are not a long-term solution due to potential side effects.
- Biologic Therapies: Biologic drugs, like anti-TNF agents (e.g., infliximab, adalimumab), work by targeting specific proteins in the immune system. They can help induce and maintain remission in Crohn’s Disease, which, in turn, can reduce pain and discomfort.
- Immunomodulators: Medications like azathioprine or methotrexate may be prescribed to modulate the immune system and reduce inflammation in the gut, which can alleviate pain in Crohn’s Disease.
- Lifestyle modifications: Changing the patient’s lifestyle can also help with pain management. Adopting a well-balanced diet that avoids trigger foods, regular exercise, and keeping a healthy mental state can alleviate symptoms and enhance overall well-being.
Conclusion About Crohn’s Disease Lifespan
It’s essential to clarify that Crohn’s Disease itself is generally not fatal. While it’s a chronic condition that requires ongoing management, it is not an immediate death sentence. Early detection is vital for effective pain management and improved life expectancy.
For individuals seeking diagnostic tests to evaluate potential inflammatory bowel disease (IBD) or related gastrointestinal concerns, schedule an appointment at Advanced Colorectal And General Surgery.
We offer a comprehensive range of diagnostic procedures, including colonoscopy and other advanced tests, to thoroughly assess your gastrointestinal health and guide you towards appropriate treatment options.
Frequently Asked Questions About Crohn’s Disease Lifespan
How Often Should Individuals With Crohn’s Disease Undergo Medical Check-Ups?
Regular follow-up appointments are essential, and the frequency depends on individual needs and disease activity.
What Support And Resources Are Available For Individuals And Families Coping With The Challenges Of Crohn’s Disease?
Support groups, patient advocacy organisations, and healthcare professionals can provide valuable support and resources.
Can Crohn’s Disease Go Into Remission, And If So, How Does This Affect Life Expectancy?
Yes, Crohn’s Disease can go into remission with appropriate treatment. During remission, the disease is less active, and individuals often experience improved quality of life, potentially extending their life expectancy.
What Foods Are Recommended For People With Crohn’s Disease?
Consuming low-fibre foods, lean proteins, cooked and peeled vegetables, ripe and peeled fruits, and dairy alternatives is generally advisable if lactose intolerant. Foods rich in omega-3 fatty acids and probiotic-rich foods like yoghurt can be beneficial.
Ulcerative Colitis: How Much Blood Is Too Much To Cause Concern?
Ulcerative Colitis is a chronic inflammatory bowel disease (IBD) that affects millions of people worldwide. Characterised by the inflammation and ulceration of the colon’s inner lining, this condition often brings along a host of uncomfortable and debilitating symptoms, including blood in the stools.
While this symptom is common among individuals with Ulcerative Colitis, how much blood is too much? Determining when it becomes a cause for concern can be challenging.
This article sheds light on the issue of blood in stools among Ulcerative Colitis patients. It explores why this symptom occurs, how to assess its severity, and most importantly, when it warrants medical attention.
When To Be Concerned About Blood In Stool
Ulcerative Colitis primarily affects the large intestine or colon. This chronic condition happens when there is an inflammation and a formation of ulcers (open sores) on the inner lining of the colon. Unlike Crohn’s disease, Ulcerative Colitis is confined to the colon and rectum.
Ulcerative Colitis can manifest with a range of symptoms, including
- Diarrhoea, often with blood or mucus
- Abdominal pain and cramping
- Urgent need to have a bowel movement
- Fatigue
- Unexplained weight loss
- Reduced appetite
- Rectal bleeding
While rectal bleeding is a common occurrence among UC patients, it should not be overlooked. Patients must be attentive to and monitor the presence of blood in their stool, as excessive bleeding can pose significant health risks. Certain warning signs and red flags should prompt immediate concern and action.
Frequent Bowel Movement And Blood In Stool: A mild flare-up may result in several daily bowel movements with intermittent blood in the stool. In more severe flare-ups, individuals may experience six or more bowel movements per day, with blood consistently present.
The copious amount of blood in your stool is definitely a concern. If you notice a significant increase in the amount of blood in your stool or if you experience continuous or heavy bleeding, it is essential to contact your healthcare provider immediately.
Signs Of Excessive Bleeding: You should also be aware of signs that suggest excessive bleeding, such as lightheadedness, dizziness, or weakness. Profuse or uncontrolled bleeding, especially if accompanied by symptoms like fainting, should be taken seriously and require immediate medical attention.
Severe abdominal pain: Intense abdominal pain, particularly if it is persistent or accompanied by bloating and distension, requires prompt evaluation.
Paleness: If you notice a marked paleness of your skin or experience symptoms of anaemia, such as persistent weakness and fatigue, it may indicate significant blood loss.
High fever: A high fever, especially if associated with chills, may suggest an infection or a complication of Ulcerative Colitis that requires immediate attention.
Change in mental status: Confusion, disorientation, or altered mental status should be taken seriously and investigated promptly.
Change in Symptoms: Pay attention to changes in your overall health and other UC symptoms. If you experience a decline in well-being, unexplained weight loss, or other new symptoms alongside rectal bleeding, it may warrant further evaluation.
Why Does Ulcerative Colitis Cause Blood In Stools?
Among the symptoms commonly associated with Ulcerative Colitis, rectal bleeding or blood in stools stands out as a significant and sometimes troublesome sign. This occurrence is intimately linked to the intricate pathophysiology of the disease.
The inflammation and ulceration in the colon can directly impact the delicate blood vessels residing within the colon’s tissues. When inflammation takes hold, it can weaken these blood vessels, which is why they are more susceptible to rupture.
As a result, even minor trauma or irritation to the colon’s lining can prompt these small blood vessels to break, leading to the leakage of blood into the intestinal contents. Consequently, the blood mixes with the stool as it traverses the colon, causing rectal bleeding.
Types Of Bleeding Associated With Ulcerative Colitis
Blood in stools can manifest in various ways for individuals with Ulcerative Colitis. They are classified into three different types of bleeding, including:
Gross Hematochezia
Gross Hematochezia refers to the noticeable and visible presence of bright red blood in the stool. The blood is usually vivid red in colour and is easily seen in the stool or on toilet paper after a bowel movement.
It is often alarming and can be a cause for immediate concern because it is easily visible, indicating active and significant bleeding from the lower gastrointestinal tract.
The duration of gross hematochezia can vary. It may be intermittent, occurring during flare-ups, or it may be persistent in cases of severe bleeding.
Occult Bleeding
Occult bleeding is less apparent, as it involves the presence of blood in stools that may not be visually noticeable. The blood is typically not bright red but may be darker in colour or even black (melena). The bleeding can be intermittent and subtle.
Occult bleeding is often detected through specialised tests like faecal occult blood tests (FOBT) or faecal immunochemical tests (FIT), which can detect small amounts of blood not visible to the naked eye.
Mucosal Bleeding
In some cases, the bleeding may be limited to the colon’s mucosal layer. This type of bleeding may result in mucus-coated stools with streaks of blood. The blood may mix with mucus, making it appear less obvious than gross hematochezia.
Mucosal bleeding can be chronic and may persist over time, necessitating ongoing management and treatment to control inflammation.
Monitoring Blood In The Stool For UC Patients

There isn’t a universally defined “normal” level of rectal bleeding in UC patients because it can vary widely. It’s important to keep track of your symptoms and let your healthcare provider know. They can help you figure out the best treatment based on your situation.
Individuals can use a simple scale to describe the amount of blood, ranging from minimal spotting to significant bleeding. This self-assessment can aid in monitoring changes in bleeding over time. While it may not replace a medical evaluation, it can provide valuable information.
- Keep a Symptom Journal: Maintain a daily or weekly journal where you record your symptoms, including details about rectal bleeding. Note the frequency, consistency, and colour of blood in your stools. Be as specific as possible to help your healthcare provider understand your symptoms accurately.
- Use the Bristol Stool Chart: This chart categorises stool types from 1 to 7, with 1 being very hard stools and seven being entirely liquid. Note where your stools fall on this scale and whether they are accompanied by blood. This can provide valuable information about changes in your bowel habits.
- Measure Blood Loss: If you notice blood in your stools, you can try to estimate the amount. For example, you might describe it as “a few drops,” “streaks,” or “a noticeable amount.” This can help you gauge the severity of bleeding over time.
- Monitor Other Symptoms: Alongside rectal bleeding, keep track of other UC symptoms such as abdominal pain, diarrhoea, fatigue, or changes in appetite. Understanding how these symptoms correlate with rectal bleeding can provide a more comprehensive picture of your condition.
- Consult Your Healthcare Provider: Share your symptom journal with your doctor during regular check-ups or when you notice significant changes in your condition. Your healthcare provider can use this information to adjust your treatment plan and ensure your UC is well-managed.
Managing UC-Associated Rectal Bleeding

Rectal bleeding is common among individuals with UC, but it’s not necessarily a severe symptom for everyone. There is no cure yet for this condition.
Fortunately, there are ways to manage its symptoms and reduce or stop rectal bleeding. This is necessary because left untreated, it increases the risk of developing colorectal cancer.
To address excessive rectal bleeding in UC, doctors recommend a combination of medications and therapies tailored to the individual’s condition and the severity of their symptoms.
Aminosalicylates: These anti-inflammatory drugs, such as mesalamine, help manage UC. They work by reducing inflammation in the colon’s lining, potentially alleviating rectal bleeding. Aminosalicylates can be administered orally or as rectal formulations, such as suppositories or enemas, for more targeted treatment.
Corticosteroids: In cases of more severe UC or during flare-ups, corticosteroids like prednisone may be prescribed. These medications are potent anti-inflammatories and are used to suppress inflammation quickly.
Immunosuppressants: Medications like azathioprine or 6-mercaptopurine modulate the immune response. They can be effective in managing UC by reducing inflammation and preventing immune-related damage to the colon. These drugs are often used when aminosalicylates are ineffective or for maintaining remission.
Biologics: Biologic agents, such as infliximab or adalimumab, are advanced treatments that target specific proteins involved in the inflammatory process. Biologics are typically prescribed to patients with moderate to severe UC cases who do not respond to other treatments. They can be highly effective in managing UC symptoms and promoting remission.
Therapy: In addition to medications, certain therapies can directly address rectal bleeding in UC. For example, mesalamine enemas or suppositories deliver the medication directly to the rectum and lower colon, providing targeted relief from inflammation and bleeding in this area. These therapies are particularly useful in cases where rectal involvement is prominent.
Surgery: In severe cases of UC or when medications prove ineffective in controlling symptoms and preventing complications, surgery may be necessary. Doctors may recommend the removal of the colon (colectomy), with or without the creation of an ileal pouch-anal anastomosis (IPAA). Surgery can provide a long-term solution for managing UC but involves significant lifestyle adjustments and potential changes in bowel function.
Colonoscopy: Colonoscopy is a diagnostic procedure that can be performed to evaluate various gastrointestinal conditions, including rectal bleeding. It allows healthcare providers to visualise the colon and rectum directly to look for abnormalities, such as inflamed tissue, ulcers, polyps, or tumours that may be responsible for the bleeding.
One of the essential purposes of colonoscopy in cases of rectal bleeding is to screen for colorectal cancer. Colorectal cancer can cause rectal bleeding, and early detection through colonoscopy is crucial for successful treatment and improved outcomes.
Conclusion About UC-Associated Rectal Bleeding
While rectal bleeding is a common symptom of UC, the level of concern depends on factors such as frequency, severity, and associated symptoms. Monitoring changes and discussing them with your healthcare provider is essential to determine their significance.
It’s essential to remember that UC is a chronic condition often requiring ongoing treatment and monitoring. With the right approach, including medications, dietary modifications, and lifestyle adjustments, individuals with UC can achieve symptom relief, maintain remission, and enjoy an improved quality of life.
It’s important for people with UC to consult with reputable healthcare professionals like Dr. QM Leong. Regular consultations with experts can greatly improve the management of Ulcerative Colitis, enhance quality of life, and lower the risk of complications.
Book a consultation today!
Frequently Asked Questions About UC-Associated Rectal Bleeding
Can Diet Changes Help Manage Rectal Bleeding In Ulcerative Colitis?
Yes, dietary modifications can be beneficial for some individuals. Avoiding trigger foods and consuming a balanced diet may help reduce symptoms, including rectal bleeding.
Are There Natural Remedies For Addressing Bleeding In Ulcerative Colitis?
While some people find relief from natural remedies like aloe vera or curcumin supplements, it’s essential to consult with a healthcare provider before trying any alternative therapies.
Can Stress Exacerbate Rectal Bleeding In UC?
Stress can potentially worsen UC symptoms, including rectal bleeding, in some individuals. Stress management techniques and lifestyle adjustments may help mitigate its impact.
How Often Should Patients Undergo Colonoscopy For Surveillance?
The frequency of colonoscopy surveillance for UC patients varies based on disease severity and duration. Gastroenterologists typically recommend regular colonoscopies to monitor for complications and assess disease activity.
Is It Anal Fissure Or Haemorrhoid? 4 Key Differences
Anal fissures and haemorrhoids are two common conditions that affect the anorectal region, causing discomfort and concern for many individuals. Though they share many similarities, such as their location and some symptoms, they have distinct causes, symptoms, and treatments, particularly when looking at what causes anal fissures and how they are typically managed in Singapore.
This article explains the differences between anal fissures and haemorrhoids and the best way to manage and treat each condition.
What Is An Anal Fissure?
An anal fissure is a small, linear tear or cut in the mucosa of the anal canal. These tears typically result from the stretching of the anal mucosa beyond its capability, often due to passing large or hard stools or other forms of trauma such as childbirth or anal intercourse.
This condition is characterised by severe pain and bleeding, especially during and shortly after bowel movements, which explains why anal fissures can cause bleeding during bowel movements.
Symptoms:
- Sharp, intense pain during bowel movements, sometimes lasting hours after.
- Bright red bleeding visible on toilet paper or stool.
- A visible tear or cut in the skin around the anus.
Risk Factors:
- Chronic constipation or diarrhoea: Repeated straining and prolonged irritation can lead to fissures.
- Childbirth: Women are at higher risk postpartum due to the pressure and stretching during delivery.
- Inflammatory bowel disease: Conditions like Crohn’s disease can make one more susceptible.
- Tight anal sphincter muscles: Can reduce blood flow to the anorectal area, making the tissue more prone to tearing.
- Age: Infants are prone to fissures, but they can occur at any age.
What Are Haemorrhoids?
Also called piles, haemorrhoids are swollen veins found in the rectal area. They can develop inside the rectum (internal haemorrhoids) or under the skin around the anus (external haemorrhoids).
Haemorrhoids are primarily caused by increased pressure in the lower rectum because of straining during bowel movements, prolonged sitting or standing, obesity, pregnancy, or a low-fibre diet.
Symptoms:
- Itching or irritation in the anal region.
- Pain and discomfort while sitting or during bowel movements.
- Swelling around the anus.
- Painless bleeding during bowel movements
Risk Factors:
- Age: As people get older, the supporting tissues in the rectum and anus can stretch and weaken, leading to an increased risk of developing haemorrhoids.
- History of Chronic constipation or diarrhoea: Straining during bowel movements is a primary cause of haemorrhoids.
- Pregnancy: The weight of the foetus can cause haemorrhoidal vessels to enlarge, along with hormonal changes. Delivery also increases pressure in these vessels.
- Prolonged sitting: Staying seated for long periods, especially on the toilet, can increase the pressure on the veins in the anus and rectum.
- Obesity: Excess weight, particularly around the midsection, can increase pressure on the pelvic veins.
- Diet: A low-fibre diet can lead to constipation, resulting in straining during bowel movements.
Distinguishing Between Haemorrhoids Vs Anal Fissures
When trying to distinguish between haemorrhoids vs anal fissures, consider the nature and location of the pain, the bleeding pattern, and any additional symptoms like itching or the presence of lumps.
Here’s a deeper look into how to differentiate the two based on pain type, bleeding patterns, and other symptoms:
1. Appearance
- Anal fissures: They are small tears that appear as linear or oval-shaped ulcers in the posterior midline of the anus. They can be hard to see without proper positioning and lighting. Rarely, they can be found anteriorly or on the sides.
The fissure can look like a fresh, red tear or a chronic, deeper ulcer with defined or raised edges. Swelling and redness may occur in the surrounding tissue if the area is irritated or infected. A sentinel pile, a tag of skin at the distal end of the fissure, can also sometimes be observed.
- Haemorrhoids: Internal haemorrhoids are not visible externally although they may prolapse and protrude outside the anal canal. External haemorrhoids appear as lumps or swelling around the anal rim and can be felt as bulges at the anal opening. Haemorrhoids can be body-coloured, slightly redder, or blueish if thrombosed.
2. Type of Pain
- Anal Fissures: The pain associated with anal fissures is typically acute and intense. It occurs during bowel movements as the stool passes the tear, causing a sharp, searing pain that can be quite severe and may be accompanied by minimal bleeding.
The pain might continue for several hours after defecation, often described as feeling like passing glass shards. Fissures can also cause a spasm of the anal sphincter, further intensifying the pain.
- Haemorrhoids: In contrast, haemorrhoids generally cause a duller, throbbing pain, especially when they are external and become thrombosed or prolapsed.
The discomfort might increase while sitting or during bowel movements but doesn’t usually reach the acute intensity of fissure pain. Internal haemorrhoids might not be painful unless they prolapse or become thrombosed.

3. Bleeding Patterns
- Anal Fissures: Bleeding is a common symptom associated with anal fissures, particularly when understanding why anal fissures can cause bleeding during bowel movements. When an anal fissure occurs, the small tear or crack in the lining of the anus can result in bright red blood during or after a bowel movement. This bleeding is typically minimal, but it can be noticeable on toilet paper or in the toilet bowl.
- Haemorrhoids: Haemorrhoids can also cause bright red bleeding, but the pattern might differ. Internal haemorrhoids often lead to painless bleeding that might be noticed as streaks on the stool or pooling in the toilet bowl. External haemorrhoids, especially when they rupture or are thrombosed, can bleed significantly and sometimes clotted blood may be noticed.
4. Itching And Discomfort
- Anal fissures: Don’t typically cause itching but can lead to significant discomfort due to the spasm of the anal sphincter muscle. These spasms can result in sharp, stabbing, or burning pain during or after bowel movements, making it uncomfortable for individuals with anal fissures to pass stools.
- Haemorrhoids: They can often lead to itching and skin irritation around the anal area, mainly when they are external, and cause swelling and inflammation of the surrounding skin.
What Happens If Anal Fissures Or Haemorrhoids Are Left Untreated?
If left untreated, both anal fissures and haemorrhoids can lead to more serious complications, especially in cases involving how chronic anal fissures develop and why they may not heal on their own. Anal fissures can develop into chronic pain, deeper fissures, and increased risk of infection.
Individuals may start avoiding going to the bathroom due to the pain, leading to constipation or impacted stools, which can exacerbate the problem.
Similarly, if left untreated, haemorrhoids can cause various complications, such as anaemia, become thrombosed, prolapsed haemorrhoids, skin tags, and infection.
Prolapsed haemorrhoids can stretch and bulge outside the anus, while thrombosed haemorrhoids can be very painful and may require surgical intervention.
Additionally, external haemorrhoids that are left untreated can lead to excess, saggy skin around the anus, known as skin tags, which can cause hygiene issues and further irritation.
Diagnosing Anal Fissure Vs Haemorrhoids

The accurate diagnosis of anal fissures and haemorrhoids involves a physical examination and other procedures by a healthcare professional. Here’s how each condition is generally diagnosed:
Anal Fissures
- Visual Inspection: A doctor will look for visible signs of a tear in the lining of the anal canal. This is often evident as a small cut or ulcer, usually located posteriorly in the midline.
- Digital Rectal Exam (DRE): This might be avoided if there’s severe pain, as it can be quite uncomfortable.
- Anoscopy: A small, lighted tube (anoscope) may be used to view the anal canal more clearly. However, this might not be possible in acute fissures due to pain.
Haemorrhoids
- Physical Examination: External haemorrhoids can often be seen or felt as swollen lumps around the anus. Internal haemorrhoids may not be apparent until they prolapse.
- Digital Rectal Exam (DRE): During DRE, the doctor may feel for abnormalities inside the rectum.
- Anoscopy or Proctoscopy: These tools are often used to view internal haemorrhoids or other causes of bleeding within the rectum.
Treatment Of Anal Fissures And Haemorrhoids
The treatment for haemorrhoids and anal fissures involves both conservative measures and, if necessary, more invasive medical procedures, including non-surgical and medical options for managing anal fissures in Singapore. Here’s an overview of the typical treatment approaches:
Anal Fissures
The treatment goals for anal fissures aim to provide relief from symptoms, promote healing, and prevent the recurrence of the conditions. Options include:
- Topical Creams: Nitroglycerin ointment or other topical creams are prescribed to help relax the muscle around the anus (the internal anal sphincter), improving blood flow to the area and facilitating healing.
- Warm Baths: Sitting in a few inches of warm water (sitz baths) several times a day can relax the sphincter muscle and promote healing.
- Dietary Changes: Doctors may suggest increasing fibre intake and fluid consumption to soften stools and reduce strain on the fissure.
- Stool Softeners: These may be recommended to reduce straining during bowel movements.
- Surgery: In some cases where conservative treatment fails, a surgical procedure known as lateral internal sphincterotomy may be performed, particularly in situations involving when surgery may be recommended for persistent anal fissures.
Haemorrhoids
These haemorrhoid treatments can help relieve symptoms like pain, itching, bleeding, and discomfort, reducing swelling and promoting healing of hemorrhoidal tissue, while also preventing recurrence and addressing complications when necessary.
- Over-the-counter Creams and Suppositories: These can reduce itching, pain, and swelling. They often contain ingredients like hydrocortisone or witch hazel.
- Cold Packs: To reduce swelling and pain, ice or cold packs must be applied to the area regularly.
- Sitz Baths: Just like with fissures, warm water baths can provide relief from itching and discomfort.
- Dietary Changes: Increasing fibre intake can prevent constipation, reducing the strain and pressure on haemorrhoids.
- Minimally Invasive Procedures: For persistent or severe haemorrhoids, a doctor may perform rubber band ligation, sclerotherapy, or infrared coagulation to reduce or eliminate haemorrhoids.
- Surgery: In severe cases, haemorrhoidectomy (removal of haemorrhoid) or haemorrhoid stapling may be necessary.
When To Seek Medical Help
Anal fissures and haemorrhoids can sometimes resolve on their own, especially if they are mild and appropriate lifestyle modifications are made. However, the healing process and likelihood of self-resolution depend on several factors, including the severity of the condition, underlying causes, and individual health and diet.
There are specific situations in which it’s advisable to seek medical help for either condition:
- Persistent Symptoms: If you have symptoms of an anal fissure, such as pain, bleeding, or discomfort, and they persist for more than a few days despite self-care measures, it’s a good idea to consult a healthcare provider. If you have haemorrhoid symptoms (pain, itching, bleeding, or swelling) that persist for more than a week despite self-care measures, consult a healthcare provider.
- Severe Symptoms: If the pain associated with the anal fissure is severe, does not improve with over-the-counter pain relief, or interferes significantly with your daily life, a medical evaluation is recommended. Meanwhile, severe pain, excessive bleeding, or prolapsed haemorrhoids (when internal haemorrhoids protrude through the anus) require medical evaluation.
- Frequent Recurrence: If you have recurrent anal fissures or haemorrhoids, it may indicate the need for treatment approaches used for long-standing or recurrent anal fissures.
- Signs of Infection: If you notice signs of infection around the anal fissure, such as increased pain, redness, swelling, or the presence of pus, prompt medical attention is necessary.
- Concerns About Cancer: In rare cases, rectal bleeding can be a sign of colorectal cancer. If you have significant rectal bleeding or bleeding associated with other concerning symptoms (such as unexplained weight loss or changes in bowel habits), it’s essential to seek prompt medical attention.
In both cases, your healthcare provider can perform a thorough evaluation, confirm the diagnosis, and recommend appropriate treatments.
Conclusion About Anal Fissures Vs Haemorrhoids
Anal fissures and haemorrhoids are two different conditions with different treatments and symptoms. Learning more about these conditions can prevent future occurrences and treat any symptoms effectively, especially with a complete overview of anal fissure diagnosis and treatment options in Singapore.
Remember, when in doubt, seek professional medical advice to get the correct diagnosis and treatment plan. At Advanced Colorectal And General Surgery, your comfort and health are our priority.
Our specialist is experienced in performing advanced surgical procedures related to the colon, rectum, and other general surgical conditions. We strive to provide the most effective and personalised treatment options to ensure the best possible outcomes for our patients. Book an appointment today!
Frequently Asked Questions About Anal Fissures Vs Haemorrhoids
Can I Still Poop If I Have Anal Fissures Or Haemorrhoids?
Yes, you can still poop with anal fissures or haemorrhoids, but it may be uncomfortable or painful. To ease discomfort, it’s important to keep stools soft and regular through a high-fibre diet, plenty of hydration, and possibly the use of stool softeners.
How Long Do Anal Fissures And Haemorrhoids Typically Take To Heal?
Acute fissures may heal within a few weeks with proper care. Chronic fissures might take longer and require medical treatment. For haemorrhoids, the healing time can vary. Mild haemorrhoids may improve within a few days, while more severe cases might take a few weeks and could recur or require medical intervention.
Are Anal Fissures And Haemorrhoids More Common At A Certain Age?
Both conditions can occur at any age but are more commonly seen in adults due to factors like increased pressure from long-term sitting, dietary habits, and, in the case of haemorrhoids, ageing-related weakening of the tissues.
Can Anal Fissures And Haemorrhoids Occur Simultaneously?
Yes, it is possible to have both anal fissures and haemorrhoids at the same time. These conditions can share similar symptoms, and a healthcare provider can help differentiate between them.