What Does A Colorectal Doctor Do? A Comprehensive Guide

what does a colorectal doctor do

“What does a colorectal surgeon do?” is a question often asked by patients who need treatment for colorectal problems.

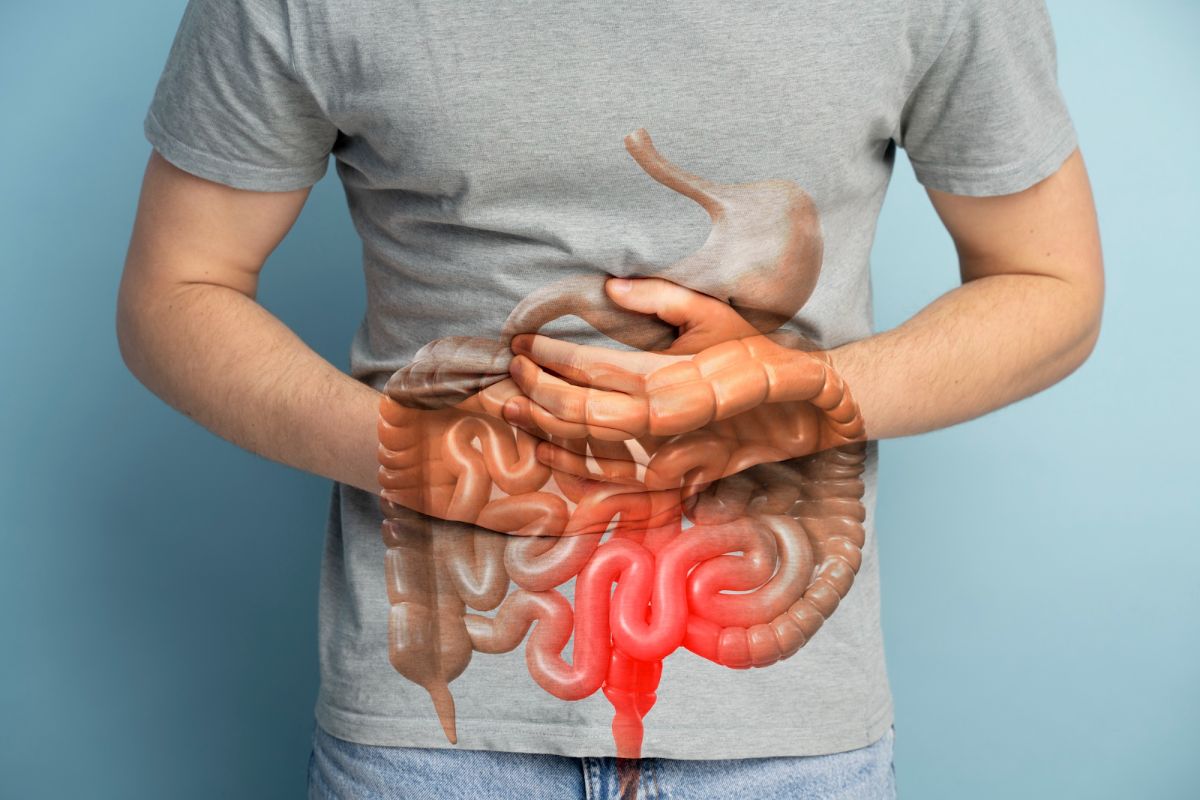
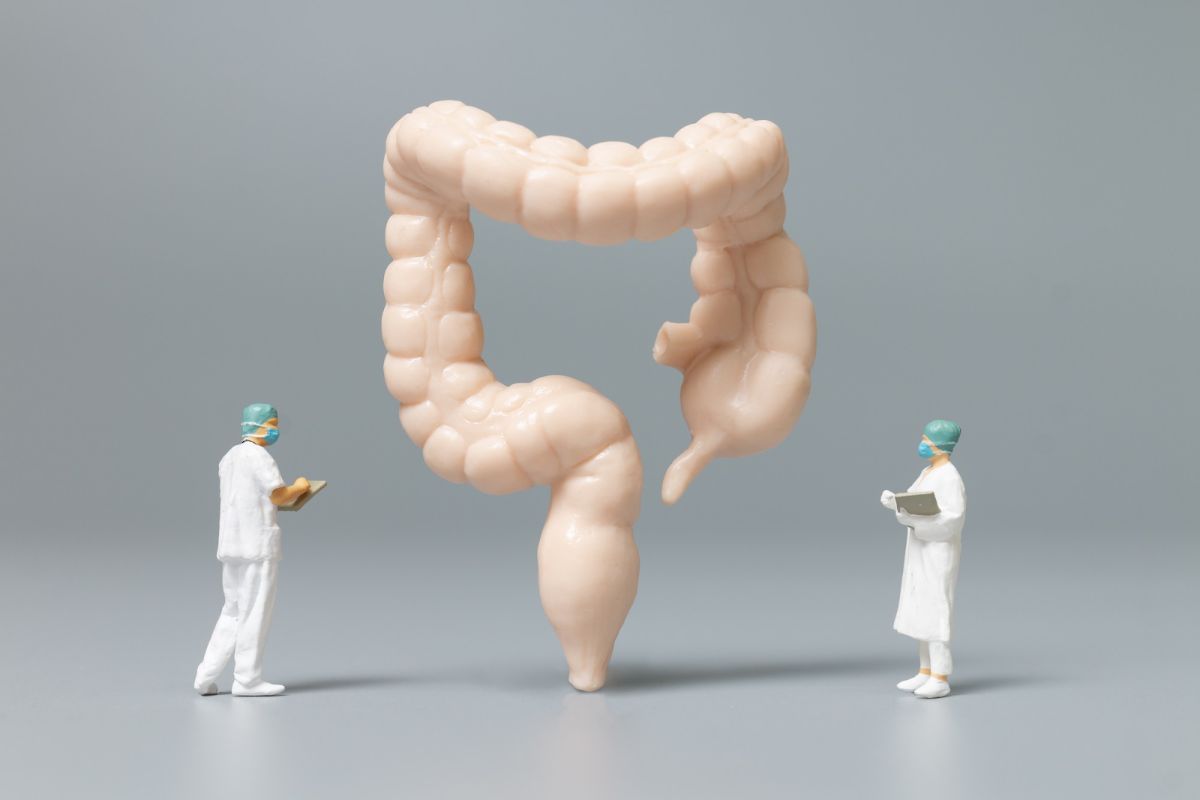
Colorectal surgeons are specialists in their field who treat, diagnose, and perform surgery on multiple conditions affecting the lower gastrointestinal tract. Also known as the GI tract, this part of the digestive system comprises the large intestine, colon, and anus.

Often, colorectal surgeons also work alongside gastroenterologists to treat conditions affecting the entire GI system. They may perform similar procedures and manage similar conditions.

When Should You Visit A Colorectal Surgeon?

What to expect from a colorectal doctor

A patient will typically consult a colorectal surgeon if they experience symptoms affecting their GI tract. Many patients start by seeing a general physician or gastroenterologist, who will later refer the patient to a colorectal doctor.

Medical conditions that will likely require treatment by a colorectal surgeon include:

  • Inflammatory Bowel Disease (IBD)
  • Colorectal cancer and polyposis
  • Peritoneal carcinomatosis
  • Hereditary nonpolyposis colorectal cancer (HNPCC)
  • Anal cancer
  • Appendix cancer
  • Anal fistulas
  • Hernias
  • Rectal prolapse
  • Perianal abscess
  • Ischemia (blood supply loss)
  • Gallstones
  • Diverticular disease
  • Ulcerative colitis
  • Appendicitis
  • Crohn’s disease
  • Rectal bleeding
  • Anal warts
  • Haemorrhoids
  • Constipation
  • Rectal bleeding/gastrointestinal bleeding

Do Colorectal Surgeons Treat Conditions That Affect Only The Large Intestine?

While colon and rectal surgeons specialise in the large intestine, they also perform advanced general surgery.

Most of our body’s organs affect each other — this is why colorectal surgeons may often treat other organs closely linked with the large intestine or share the same conditions.

Other organs which a colorectal surgeon may treat include:

  • Urinary tract
  • Stomach
  • Small intestine

What Qualifications Does A Colorectal Surgeon Have?

Board-certified colon and rectal surgeons will at least have completed a five-year training program in general surgery and additional training at an ACGME-accredited (Accreditation Council for Graduate Medical Education) colon and rectal surgery residency.

In addition to their proficiency in general surgery, colon and rectal surgeons also have specialised skills in performing endoscopies of the rectum and colon. They can also perform anorectal physiology techniques to examine and diagnose anal sphincter and pelvic floor disorders.

Many colorectal surgical residency programs offer training in minimally invasive surgery of the abdomen, including the rectum and colon.

What's The Difference Between A Colorectal Surgeon And A General Surgeon?

1. Specialty

The primary difference between a general and a colorectal surgeon is the level of depth and knowledge in treating specialised conditions. 

General surgeons are typically trained in general GI tract surgery. Meanwhile, a colorectal surgeon has received in depth training in bowel surgery, especially in the colon and rectum.

2. Availability

General surgeons are available in many public hospitals and centres. While you can still find a colorectal surgeon in public health centres and communities, many opt for private practice. 

3. Minimally Invasive Surgery

In urgent cases, a general surgeon is less likely to perform laparoscopic surgery than a colorectal doctor. The latter can comfortably perform minimally invasive surgery, especially for patients requiring emergency attention. 

This is because they have a professional understanding and experience in advanced IBD principles and techniques, which a general surgeon does not have.

What Techniques Do Colorectal Surgeons Use?

What Techniques Do Colorectal Surgeons Use?​

Colorectal surgeons use various surgical and endoscopic techniques to treat their patients’ GI tracts. They have all the right equipment and tools to treat complex conditions, either through endoscopy, minimally invasive surgery, or open surgery.

Some techniques done by colorectal surgeons include:

  • Colonoscopy – Examination of the digestive system (colon lining and rectum) to detect irregularities in the bowel and determine possible symptoms of colorectal cancer.
  • Sigmoidoscopy – Diagnostic test for examining the sigmoid colon (lower part of the large intestine or colon), which is close to the anus and rectum. This may be done to get a tissue sample (biopsy) and diagnose symptoms such as diarrhoea, constipation, polyps, bleeding, abdominal pain, etc.
  • Laparoscopic surgery – A minimally invasive surgery allowing a doctor to make small, 0.5 to 1.0 cm cuts on the patient to treat conditions that may develop inside the abdomen or pelvis.
  • Gastroscopy– Non-surgical procedure to examine a person’s upper digestive system. 

Aside from advanced surgery techniques, a colorectal surgeon can also perform different procedures, including:

  • Endoscopic mucosal resection (EMR) or endoscopic submucosal dissection (ESD) – Removal of difficult tumours.
  • Polypectomy – Surgical removal of polyps from the intestines.
  • Bowel resection surgery – Removing the entire large bowel or parts of it. This surgery is also known as a colectomy.
  • Ostomy surgery – An operation that redirects bowel contents to a stoma or an opening outside the abdomen connecting to the digestive system.
  • Appendicectomy – Removal of an infected or inflamed abdomen.
  • Anastomosis surgery – Reversal of an ostomy. This procedure reconnects the colon to the remainder of the rectum after most of it has been removed through colorectal cancer surgery.
  • Rectopexy – Repair of rectal prolapse. It can be performed through an abdominal incision or keyhole surgery.
  • Lateral internal sphincterotomy – Operation to treat an anal fissure or a tear in the anal opening which can cause itching, pain, and bleeding.
  • Hernia repair – Surgical procedure for fixing a hernia (herniorrhaphy).
  • Open and stapler haemorrhoidectomy – Excision of excess haemorrhoid tissue by lifting and returning it to its original position.

Conclusion On What Colorectal Surgeons Do

The domain of a colorectal surgeon lies in treating, diagnosing, and conducting surgery on medical conditions affecting the lower GI tract.

Although not all colorectal conditions need surgical treatment, visiting a colorectal specialist is advised, as they can treat your condition more effectively.

Dr Q.M. Leong is a colorectal surgeon in Singapore with decades of experience in his field. He specialises in treating haemorrhoids, gallbladder diseases, peptic ulcer, diverticular disease, and other GI diseases.

Need a colonoscopy screening? Book a consultation now or visit his colorectal clinic at:

Mount Alvernia Hospital
Medical Centre A
820 Thomson Road #01-06
Singapore 574623

Clinic Hours:

Monday to Friday, 8:30am – 12:30pm, 2pm – 5:00 pm
Saturday: 8:30am – 12:00pm
Sunday and Public Holidays: Closed

Frequently Asked Questions About
What Colorectal Surgeons Do

Why Would You Need To Be Referred To A Colorectal Surgeon?

There are different instances where a general surgeon may refer you to a colorectal doctor. For example, you’ll need to visit a surgeon if they discover a large polyp in your stomach which can’t be removed through an endoscopy. The doctor may also refer you to a colorectal surgeon for a colon cancer diagnosis.

Colorectal surgeons can treat benign and malignant conditions and perform routine colon screening and surgery when needed. Meanwhile, a gastroenterologist is a doctor who has completed internal medicine training and gastroenterology.

It is possible to feel painful sensations that come and go away a few days after undergoing colorectal or bowel surgery. You may experience the following:

  • Bowel cramps
  • Tenderness due to incision
  • Flu-like symptoms
  • Low-grade fever
  • Nausea

Depending on the procedures and techniques, many patients need to recover for several days in the hospital after colorectal surgery. They may need 3-6 weeks of recovery at home.

Yes. Contact a colorectal surgeon in Singapore if you experience irritable bowel syndrome symptoms such as:

  • Bloating
  • Constipation
  • Diarrhoea
  • Stomach cramps
  • Frequent need for bowel movement
  • Flatulence (excessive farting)

Anal Warts: Risks, Causes, Symptoms, and Prevention

anal warts

Anal warts are a form of genital warts that appear inside or near the anus. Also known as condyloma cuminata, anal warts result from the Human Papilloma Virus (HPV). HPV is one of the most common sexually-transmitted diseases passed through direct contact. Warts first appear as small growths and may grow larger and occupy the entire anus.

Most cases of anal warts don’t result in any discomfort or painful sensations. Most patients won’t even know if they eventually develop these genital warts. But if the clumps grow much more prominently later on, they may lead to itchiness, bleeding, and a mucus discharge in some cases.

What Are The Causes Of Anal Warts?

Genital warts can look like small, flesh-coloured bumps that cover the part of the skin affected. They usually appear after a sexual encounter with an HPV-infected person. HPV may go away after some time for younger individuals and may not even lead to any visible signs and symptoms. However, the virus may stay longer in the body. It may also lead to the development of cancerous or non-cancerous genital warts.

A carrier transmits HPV through direct contact with the mouth, penis, vagina, or anus. However, sexual intercourse is unnecessary for the infection to spread. Individuals can pass HPV to another through direct skin-to-skin contact. Even if the warts are invisible or not yet formed, HPV contraction is still possible.

Who Are At Risk Of Anal Warts?

In general, men and women who have a sexually active lifestyle may get anal warts. A person increases their chances of spreading or contracting anal warts if:

  • They’re consistently engaged in unprotected sex (not using any condoms or dental dams)
  • They’re promiscuous or have multiple sexual partners all at once
  • They frequently engage in anal/vaginal intercourse
  • They’re sexually active at a young age
  • They’ve had sexual relations with an HPV-carrier
  • They have an immunocompromised immune system due to a chronic illness or medication

What Are The Symptoms Of Anal Warts?

small bumps around the anal area and are no bigger than a pinhead

Anal warts often begin as small bumps around the anal area and are no bigger than a pinhead. They’re usually too small to notice but can accumulate into large clumps over time. The clusters may match the colour of the surrounding skin tissue or maybe yellowish or pinkish. 

Painful sensations or discomfort on the anus don’t usually accompany anal warts. Symptoms are rare, but there may be itchiness or a lumpy feeling around the anal region. 

Other forms of genital warts can also appear simultaneously as anal warts. In women, the clusters may develop on the vagina, vulva, or cervix. Meanwhile, men can develop genital warts on the inside of their thighs, groin, scrotum, or penis. 

If someone has engaged in oral sex with someone who has anal warts, this could also lead to a mouth infection. Warts may develop on the insides of the mouth or throat. Although benign, warts may make it difficult for the person to swallow or breathe properly due to partially blocked airways.

How Do Doctors Diagnose Anal Warts?

A doctor or colorectal specialist may diagnose anal warts by examining the anus. The patient will undergo an anoscopy. The doctor places a small tube to observe the lining of the anus and rectum. Through a visual inspection, they can determine the presence of anal warts. 

If the patient isn’t responding to treatment well, the doctor may conduct a biopsy or request tissue samples. The reason is that HPV-infected individuals with anal warts are more prone to anal cancer.

What Is The Treatment For Anal Warts?

Treatment for anal warts can be invasive or non-invasive. A colorectal surgeon can surgically remove warts, or they can prescribe topical medications to the patient. In non-severe cases, warts go away on their own, and the individual may choose not to have them treated further.

Topical Medications

For small, non-cancerous anal warts, a doctor may recommend home treatment in the form of topical medication. Common medications for anal warts include podophyllin, trichloroacetic, and bichloroacetic acid. After applying the cream or gel, the patient may feel burning or discomfort for a few minutes. But they can resume daily activities immediately afterwards.

Some topical creams and gels may irritate the affected anal region. If you experience these, stop using the cream immediately and contact your colorectal physician.

Cryotherapy Or Burning

A doctor applies the liquid nitrogen to warts during cryotherapy to remove them. This procedure causes the tissues to freeze and eventually fall off.

Alternatively, the doctor may cauterise anal warts. Cauterising is done by “burning” the warts. The doctor will apply an acidic solution to destroy the tissue. 

Surgery

If anal warts have become enlarged, the doctor can recommend a surgical procedure. The doctor will put the patient under general anaesthesia and then cut away the clumps using these instruments:

  • Surgical blade
  • Heated instrument
  • Laser.

After surgery, the patient may need to take time away from work or school to recover. They may also need to return to the doctor for a few more rounds of surgery. This is the case if there are too many anal warts to remove in just one session. 

How To Prevent Anal Warts?

Get tested before and after engaging in sexual intercours

Since the HPV virus stays in the body often without any warning signs, you can protect yourself from it (and anal warts) by taking these precautions:

  • Get tested before and after engaging in sexual intercourse
  • Avoid sexual contact with people who have anal or genital warts
  • Always use protection when having sex
  • Limit sexual contact to only one partner
  • Get HPV vaccination to protect against this STD

Conclusion

Anal warts are a type of genital warts that form in the anus. An HPV-infected individual can pass warts onto others through direct skin contact. 

In this guide, we’ve covered some basics about anal warts, including risk factors, prevention methods, symptoms, and causes. If you or someone you know has anal warts, it’s not a cause for concern as they go away over time. However, if you want to make sure you’re healthy, you can contact a trained colorectal surgeon in Singapore for treatment.

Dr Leong Quor Meng is a colorectal surgeon in Singapore specialising in colorectal cancers, hemorrhoids, anal fissures, hernias, and other related medical conditions. Get in touch with us now and tell us how we can help you.

Frequently Asked Questions About Anal Warts

A trained colorectal specialist can tell the difference between anal warts and haemorrhoids. Warts appear in clumps and feel rougher to the touch. Meanwhile, haemorrhoids, which are enlarged blood vessels, tend to be smoother.

If you can’t identify them yourself, it’s best to get in touch with a specialist who can examine and diagnose your colorectal condition.

No, anal warts aren’t usually painful. A person with anal warts can still do their day-to-day activities without being hampered.

Anal warts caused by HPV infections will go away after a few months or years. However, this doesn’t mean that the virus is no longer present in your body. As much as possible, get treatment for anal warts. Treatment prevents them from spreading and growing into larger and potentially painful clumps.

Endoscopy in Singapore – What It Is and Why It Is Done

Detailed Guide to Endoscopy Procedure Singapore

If you’re dealing with ongoing stomach discomfort, reflux, bloating, or unexplained digestive symptoms, an endoscopy in Singapore is usually the next step. It helps your doctor look directly at what’s going on inside your digestive tract, instead of guessing based on symptoms alone.

Why You May Need an Endoscopy in Singapore

You may be advised to undergo an endoscopy procedure in Singapore if you have ongoing digestive symptoms that are not settling or are difficult to clearly explain based on the initial assessment. 

In many cases, occasional stomach discomfort, nausea, or indigestion may not be serious on their own, but when symptoms persist or become more frequent, further evaluation is often recommended.

An endoscopy in Singapore allows a specialist to look directly at your upper or lower digestive tract to better understand what is causing your symptoms. It also helps doctors figure out whether further treatment or monitoring is needed.

Common reasons to consider an endoscopy include:

  • Persistent abdominal pain or discomfort
  • Rectal bleeding or blood in stool
  • Ongoing reflux, heartburn, or indigestion
  • Unexplained weight loss
  • Abnormal blood test or imaging results
  • Excessive bloating or changes in bowel habits

Beyond symptom evaluation, an endoscopy procedure in Singapore may also be used to:

  • Identify the cause of digestive symptoms such as bleeding, pain, or bloating
  • Assess the severity of existing gastrointestinal conditions
  • Screen for conditions such as colorectal cancer or precancerous changes
  • Take small tissue samples (biopsy) for further analysis
  • Remove benign polyps if needed during the same procedure
  • Monitor known or suspected gastrointestinal conditions

What Conditions Can Be Diagnosed with Endoscopy

With an endoscopy procedure in Singapore, a specialist can directly examine the digestive tract to identify a range of conditions that may be causing your symptoms. It also allows for targeted testing, including taking a small biopsy if something needs closer analysis.

Conditions that can be detected include:

  • Inflammation of the oesophagus, stomach, or intestines (such as gastritis or oesophagitis)
  • Stomach or duodenal ulcers
  • Gastrointestinal infections, including bacteria such as H. pylori
  • Polyps in the stomach or colon
  • Gastroesophageal reflux disease (GERD)-related changes
  • Sources of gastrointestinal bleeding (upper or lower tract)
  • Signs of colorectal cancer or precancerous changes
  • Coeliac-related or malabsorption-related changes in the intestinal lining

Types of Endoscopy Procedures Offered in Singapore

Affordable Endoscopy Cost Singapore - Quality Care

An endoscopy procedure in Singapore is not a single test for everyone. The type recommended depends on where your symptoms are coming from and what your doctor needs to investigate.

Upper Endoscopy (Gastroscopy)

A gastroscopy is used to examine the oesophagus, stomach, and upper part of the small intestine.

It is commonly recommended when you have symptoms such as:

  • Persistent heartburn or reflux
  • Stomach pain or discomfort
  • Difficulty swallowing
  • Unexplained nausea or vomiting
  • Suspected ulcers or inflammation
  • Unexplained weight loss

Lower Endoscopy (Colonoscopy)

A colonoscopy allows direct examination of the colon lining and can also include biopsy or removal of polyps during the same procedure if needed.

It is commonly used when there is:

  • Rectal bleeding or blood in stool
  • Changes in bowel habits (constipation or diarrhoea)
  • Persistent abdominal pain or bloating
  • Unexplained weight loss
  • Suspicion of polyps or colorectal cancer

Sigmoidoscopy (Short Examination of Lower Colon)

A sigmoidoscopy is a shorter form of lower endoscopy that examines only the lower part of the large intestine (sigmoid colon). In some cases, it is used as an initial assessment before deciding if a full colonoscopy is necessary.

It may be recommended when:

  • Symptoms are limited to the lower bowel
  • A full colonoscopy is not immediately required
  • There is rectal bleeding or suspected localised inflammation
  • A quick evaluation of constipation or bowel changes is needed

Endoscopy Cost and Price in Singapore

The cost of an endoscopy in Singapore depends on what your doctor is investigating and whether any additional procedures are needed during the same session.

In general, the endoscopy price in Singapore is usually around SGD 800 to SGD 3,500+, depending on complexity and setting.

What Affects the Price of an Endoscopy in Singapore?

Several factors influence the final cost:

  • Type of procedure (gastroscopy, colonoscopy, etc.)
  • Whether biopsies are needed 
  • Sedation or anaesthesia required
  • Specialist and facility fees
  • Hospital or day surgery setting

Read on to learn more about factors affecting endoscopy prices in Singapore. 

Can Medisave or Insurance Be Used for Endoscopy?

In many cases, Medisave and insurance can be used if the procedure is medically indicated. Coverage varies depending on your plan, and you can go through this with the clinic before the procedure, so there are no surprises.

Doctor discussing endoscopy costs with a patient

What to Expect During an Endoscopy in Singapore

The procedure is straightforward, and most steps are planned to keep you comfortable and safe.

Before the Procedure

  • You will usually be asked to fast for at least six hours before the endoscopy (or as instructed by your doctor)
  • This ensures the stomach is empty for a clearer and safer examination
  • If a colonoscopy is planned, a laxative may also be given to clear the bowels
  • A local anaesthetic may be applied to reduce discomfort
  • Sedation is given to help you stay relaxed and comfortable

During the Procedure

  • A thin, flexible camera is gently inserted into the relevant part of your digestive tract
  • The doctor examines the area in real time on a monitor
  • The procedure typically takes around 15 to 30 minutes, depending on findings

After the Procedure (immediate monitoring)

  • You will be observed for one to two hours until the sedation wears off
  • In some cases, longer observation may be needed if treatment was done during the procedure

Recovery After an Endoscopy Procedure

After your endoscopy procedure in Singapore, you’ll be monitored until the sedation wears off. Most people go home the same day.

You might feel a bit bloated or drowsy, and if you had a gastroscopy, your throat may feel slightly sore. This usually settles within a day or two. You should be able to eat and return to normal activities fairly quickly, depending on how you feel.

Read on to find out more about what to expect during an endoscopy in Singapore.

Is Endoscopy Safe and Painful?

If you’re worried about an endoscopy in Singapore, that’s completely normal. Most patients feel anxious before the procedure, but endoscopy is generally safe and well-tolerated, especially with sedation used throughout. 

Sedation helps keep you relaxed, and most patients do not feel pain during the procedure. Many also have little or no memory of it afterwards. The focus is always on making the experience as comfortable as possible while allowing accurate diagnosis.

After the procedure, it’s common to experience mild bloating, which usually settles fairly quickly. If you had a gastroscopy, you may also notice a slight sore throat. Most of these symptoms are temporary and typically resolve within 24 to 48 hours.

Risks and Complications

  • Mild reaction to sedation
  • Minor bleeding, especially if a biopsy is taken
  • Infection (rare)
  • Perforation in the digestive tract (very rare)

These risks are rare, and your endoscopy specialist will explain them before the procedure so you know what to expect.

Choosing an Endoscopy Specialist in Singapore

When you’re deciding on an endoscopy specialist in Singapore, it’s worth looking at more than just location.

What matters is:

  • Experience in performing endoscopy procedures regularly
  • Ability to interpret findings accurately
  • Clear explanation of results and next steps
  • Access to both diagnosis and treatment if needed
  • Continuity of care if follow-up is required

Getting an Endoscopy in Singapore

If your symptoms have been lingering or affecting your daily life, an endoscopy in Singapore can give you clarity sooner rather than later.

At Advanced Colorectal and General Surgery Clinic, Dr Leong Quor Meng provides assessment and management for a wide range of digestive conditions, including endoscopy procedures. The first step is usually a consultation, where he’ll go through your symptoms and decide whether an endoscopy procedure in Singapore is appropriate for you, and what the next steps should be.

If you have persistent symptoms or need further evaluation, you can arrange a consultation for your condition.

Endoscopy Singapore Price - Transparent Rates

Frequently Asked Questions About Getting An Endoscopy In Singapore

A few factors can impact the overall cost of an endoscopy, including the type of endoscopy being performed, the extent of the procedure, and the specific clinic or hospital in Singapore where it is done. Costs can also vary based on whether biopsies or other procedures are conducted during the endoscopy.

In Singapore, the cost of an endoscopy can range from SGD 1,000 to SGD 3,000 or more. This range includes factors such as the type of endoscopy, the use of sedation, and any additional procedures or tests required.

Typically, the cost of an endoscopy in a private clinic is higher than in a public hospital. Private clinics often charge more due to shorter waiting times, more personalised care, and enhanced facilities. On the other hand, public hospitals in Singapore may offer lower prices due to government subsidies and larger-scale operations, but they might have more extended waiting periods for non-emergency procedures.

The costs of necessary medications after an endoscopy can vary. Common medications might include pain relievers, antibiotics to prevent infection, or medications to manage conditions diagnosed during the procedure. These costs are usually not included in the initial procedure fee and can range from minimal to several hundred dollars.

Results from an endoscopy can be available immediately if the procedure is diagnostic, such as visualising the gastrointestinal tract. However, if biopsies or lab tests are conducted, it typically takes several days to a week to receive the results.

Endoscopy specialists in Singapore are trained to handle complications that may arise during the procedure. They closely monitor the patient’s vital signs and are prepared to manage issues such as bleeding, perforation, or adverse reactions to sedation. In the event of a complication, the specialist will immediately stabilise the patient and provide appropriate treatment.

An endoscopy specialist in Singapore can provide dietary and lifestyle advice after the procedure. Based on the examination, the specialist may recommend changes to the patient’s diet, suggest lifestyle modifications, or prescribe medications to manage diagnosed conditions. 

Endoscopy prices in Singapore can change periodically due to fluctuations in clinic operating costs, medical supply prices, and updates to healthcare regulations. Other factors such as advancements in endoscopy technology, changes in insurance coverage policies, and adjustments in government subsidies can also influence price changes.

Several factors may result in higher cost of endoscopy in singapore, including the type of procedure (gastroscopy, colonoscopy, or specialised endoscopy), whether sedation is required, the reputation and experience of the doctor, and the facility where the procedure is performed (private vs public hospital). Additional diagnostic tests, biopsies, or polyp removal during the procedure can also increase the overall cost.

In most cases, consultation fees are separate from the endoscopy procedure itself in Singapore. Typically, you’ll be required to pay for a pre-procedure consultation to assess your condition and a follow-up consultation to review the results. It’s important to check with your clinic to understand what is covered.

More complex medical conditions often require additional steps during an endoscopy, such as biopsies, polyp removal and the use of specialised equipment. This can increase the overall cost of the procedure. Complex cases may also necessitate a longer procedure time or the involvement of multiple specialists, further influencing pricing.

Ligation Of Hemorrhoids: 7 Things To Understand

Ligation of hemorrhoids

Hemorrhoids is a common disease characterised by swollen blood vessels in the anus or lower rectum. Hemorrhoids can occur from straining during bowel movements or sitting for long periods on the toilet. All these can lead to increased pressure in the lower rectum, causing perianal swelling.

Different treatment options are available for hemorrhoids, such as over-the-counter creams and suppositories or tablets.

Another method is rubber band ligation of hemorrhoids. This option is available only for those suffering from internal hemorrhoids, and not external hemorrhoids.

1. What Is Ligation Of Hemorrhoids?

Rubber band ligation of hemorrhoids involves tying off the hemorrhoid at its base using a rubber band. This effectively restricts the blood flow to the hemorrhoid and causes it to fall off after 7 to 10 days.

As mentioned, rubber band ligation is only for the treatment of internal hemorrhoids, wherein the swollen blood vessels develop inside the rectum.

Symptoms don’t usually manifest for internal hemorrhoids, but painless bleeding during bowel movements is the most common symptom. Trace amounts of blood may appear on the toilet or tissue.

In such cases, the doctor may require hemorrhoid banding, especially when the patient reports other symptoms like prolapse.

2. Rubber Band Ligation Procedure For Hemorrhoids

rubber band ligation procedure for hemorrhoids

To perform rubber band ligation, your doctor will insert an anoscope into your anal canal, allowing them to examine the hemorrhoid.

The doctor inserts a special instrument similar to a syringe but without the needle. It’s a safe and single-use device which sucksthe hemorrhoid tissue into the ligator.

The hemorrhoid is clasped with a small device to keep it in place. It will then wrap a rubber band around the hemorrhoid’s base, cutting off the blood flow and falling after several days.

Most rubber band ligation procedures occur in the endoscopy centre for about 5 minutes.. Patients may go home after the procedure and may continue with day-to-day activities. 

3. Preparation For Hemorrhoid Banding

Before the hemorrhoid ligation, your doctor will provide pre- and post-procedure care instructions and teach you what to do.

Make sure you go over and follow them thoroughly on your own. This ensures a smooth-sailing procedure with minimal-to-no complications.

Consult with your doctor for any additional questions or concerns about the procedure. They’ll clarify everything with you beforehand for your peace of mind.

Due to the simplicity of hemorrhoid banding, you don’t need to undertake special preparations. You don’t have to fast or refrain from a high fibre diet to clear your bowels.

However, if you’re taking blood thinners, your doctor may advise you to stop taking them at least 7 days before the ligation or depending on the medication. This is to prevent excessive bleeding during the procedure.

Make sure to arrive on time for your scheduled appointment. You may have a friend or family member accompany you for added convenience.

4. What To Expect After Rubber Band Ligation?

What To Expect After Rubber Band Ligation

Once the procedure is over, you may feel slight discomfort and fullness in your lower belly.

Some patients also report feeling like they need to take a bowel movement. All of these discomforts should go away several days post-operation. The doctor may prescribe pain medicine for added relief.

In the meantime, your doctor will ask you to refrain from doing any heavy lifting and sexual intercourse after the surgery. This is so you can make a full recovery and prevent other complications from arising.

5. Why Rubber Band Ligation Is Done

Rubber band ligation is a standard treatment for internal hemorrhoids. Patients who show symptoms even after several treatments may need to undergo surgery.

Rubber band ligation can’t be performed if not enough tissue is present for the ligator to pull.

Similarly, rubber band ligation may not be appropriate for third or fourth-degree hemorrhoids, wherein the hemorrhoid protrudes from the anus.

6. Effectiveness Of Rubber Band Ligation For Hemorrhoids

Hemorrhoid banding is a simple and safe procedure for treating first, second, and third degree hemorrhoids.

Further, the success rate for rubber band ligation ranges from 60% to 80%. Many patients who have undergone this procedure reported significant improvement in their overall quality of life.

7. Possible Complications After Rubber Band Ligation For Hemorrhoids

Possible Complications After Rubber Band Ligation For Hemorrhoids

Here are some common post-treatment complications after rubber band ligation:

  • Bleeding – There may be minor spotting when the hemorrhoid shrinks, which is normal and not a cause for concern. However, if you experience periodic bleeding, consult with your doctor for treatment.
  • Urinary retention – You may have difficulty urinating after rubber band ligation. These complications usually begin within 24 hours after the procedure. Call your doctor, take some pain killers and be sure to monitor and make regular follow-ups regarding your condition.
  • Infection in the anal region – Ligation of hemorrhoids rarely cause infection. Once again, call your doctor before trying out any at-home remedies.

Conclusion About Ligation Of Hemorrhoids

Hemorrhoid banding is a virtually pain-free surgery that removes internal hemorrhoids. The procedure takes 5 minutes to perform, allowing patients to go home on the same day.

For more information on hemorrhoid banding or hemorrhoids surgery in Singapore, contact Dr Leong Quor Meng and set an appointment today.

He is a colorectal surgeon in Singapore specialising in treating hemorrhoids, gallbladder, peptic ulcer, gastritis, hernia, anal fistulas, abscesses, diverticulitis, and other changes in bowel habits.

Frequently Asked Questions About Ligation of Hemorrhoids

Is Hemorrhoid Ligation Painful?

No, banding is relatively painless. But often patients experience some discomfort and feel they need to pass motion after banding. This sensation should improve after 24 hours.

The recovery time for hemorrhoid banding will depend on the patient and the number of hemorrhoids for ligation. But it takes one to two weeks on average before the tissue fully heals. You may speed up the recovery process by refraining from strenuous activities like

  • Weight lifting
  • Aerobic exercises
  • Jogging
  • Biking

After the procedure, you may feel the urge to take a bowel movement. However, you’re strongly advised not to empty your bowels to prevent loosening the band off the hemorrhoid.

Hemorrhoid ligation is the most effective treatment for internal hemorrhoids. When done by an experienced colorectal surgeon, you can expect a low recurrence rate of 25%.

No. Haemorrhoid ligation is normally done immediately after a colonoscopy and hence you will still be asleep while the ligation is being done.

Can Crohn’s Disease Kill You? Understand The Risks

Man with highlighted abdominal pain from Crohn's disease

Characterised by chronic inflammation in the gastrointestinal (GI) tract, Crohn’s Disease is an  (IBD) that affects millions of individuals worldwide and poses unique challenges. 

The question is, can Crohn’s Disease kill you? The short answer is no. The disease itself is not fatal, but certain complications can be life-threatening. 

This article explores Crohn’s Disease in-depth, shedding light on what it is, potential causes, and the often subtle signs that may signal its presence. We’ll also tackle several factors that impact life expectancy for those affected by this chronic condition.


What Is Crohn’s Disease?

Crohn’s Disease is a medical condition characterised by long-lasting and chronic inflammation in the gastrointestinal (GI) tract. This inflammation can occur in different parts of the digestive system, including the mouth, anus, and other area. 

The symptoms of Crohn’s Disease may vary in intensity from one individual to another, depending on the severity of inflammation.


Risk Factors Of Crohn’s Disease

Despite extensive research, the exact cause of Crohn’s Disease remains elusive. However, there are several recognised factors that contribute to its development, including genetic predisposition, environmental influences, and an abnormal immune response. 

  • Genetic Predisposition: Individuals who have family members or relatives with this disease are at higher risk. If one parent has Crohn’s disease, the risk for their child to develop the condition is estimated to be around 7-9%. If both parents have it, the risk goes up to 35% or more. 
  • Environmental Factors: Dietary choices, smoking, and exposure to infections may contribute to the development or exacerbation of Crohn’s Disease in susceptible individuals. For example, diets high in fat or refined foods and low in fibre can affect the composition and function of the gut microbiota, potentially leading to increased gut inflammation, and influencing the severity and frequency of flare-ups.
  • Abnormal Immune Response: An overactive immune system can mistakenly target the GI tract, triggering chronic inflammation. The resulting inflammation damages the intestinal walls and can lead to various symptoms associated with Crohn’s disease.
  • Age and Gender: Crohn’s Disease is most commonly diagnosed in people between 15 and 35 years old. It affects both men and women, although some research suggests that it may be more prevalent in females.
  • Ethnicity: While Crohn’s Disease occurs in people of all ethnic backgrounds, it is more common in individuals of Ashkenazi Jewish descent and historically in North America and Europe. Recent trends show increasing cases in African, Hispanic, and Asian populations, possibly due to changes in lifestyle and environment. 


Common Symptoms Of Crohn’s Disease To Look Out For

The thing about the symptoms of this inflammatory bowel disease is that they develop gradually, making them easy to dismiss or attribute to other diseases. 

However, it’s essential to pay attention to these symptoms, especially if you have one or more of the above-mentioned risk factors as left unchecked; they can worsen over time. Here are some sneaky signs of Crohn’s Disease to be aware of:

Persistent Abdominal Pain

Chronic or recurrent pain in the abdomen is one of the signs of IBD. This pain can range from mild discomfort to severe cramping and may be mistaken for indigestion or other gastrointestinal issues. 

Unlike normal indigestion where the pain is usually felt in the upper abdomen and is more generalised, abdominal pain associated with Crohn’s disease often occurs in the lower right side of the abdomen. However, it can also affect various areas within the GI tract.

Diarrhoea And Blood In Stool

Diarrhoea from Crohn’s disease is chronic and can be severe, leading to dehydration and nutrient deficiencies. It is usually accompanied by abdominal pain and may contain blood or mucus due to the inflammation and ulceration of the intestinal walls. This differs from typical diarrhoea, which might be acute, related to an infection or dietary indiscretion, and resolves in a few days.

Meanwhile, rectal bleeding in Crohn’s disease is usually a sign of inflammation or ulceration in the colon or rectum. It can range from small amounts of blood on the toilet paper to significant bleeding evident in the stool. 

The bleeding is persistent and often accompanied by other symptoms of Crohn’s disease. In contrast, normal rectal bleeding, such as that from haemorrhoids or minor anal fissures, might be occasional and not associated with chronic intestinal inflammation.

Unexplained Weight Loss

Many individuals with Crohn’s Disease experience unexplained weight loss, even when they haven’t intentionally changed their diet or exercise habits. This is often due to malabsorption of nutrients in the inflamed digestive tract and reduced appetite.

While intentional weight loss typically results in a healthier and more controlled change in physique, weight loss due to Crohn’s disease is often rapid, unintended, and associated with signs of malnutrition and illness, leading to a more unwell appearance.

Fatigue And Weakness

Chronic inflammation associated with Crohn’s Disease can lead to fatigue and weakness, which may be attributed to stress or lack of sleep. Patients with this condition have low energy and often feel their exhaustion is never-ending and not going away despite rest.

Extraintestinal Symptoms

Crohn’s Disease doesn’t only affect the digestive tract; it can also have extraintestinal manifestations that affect other parts of the body. These can include:

  • Joint Pain: Arthritis or joint pain, especially in the knees, wrists, or ankles, can occur in individuals with Crohn’s Disease.
  • Skin Problems: Skin conditions like rashes, ulcers, or erythema nodosum (painful red nodules) can be related to Crohn’s Disease.
  • Eye Inflammation: Inflammation of the eyes, known as uveitis, can occur in people with Crohn’s Disease, causing redness, pain, and vision problems.


Factors That Can Affect Lifespan For Patients With Crohn’s Disease

While Crohn’s Disease presents challenges, it is not a death sentence, and many individuals with the condition lead long, fulfilling lives. In fact, a 2022 study in Sweden shows that the net survival of people with Crohn’s Disease has improved significantly compared to past decades. 

It was 54% for those diagnosed between 1963–1985, 88% for those diagnosed between 1986–1999, and up to 93% for individuals diagnosed between 2000–2010.

However, several factors can influence how long you can live with Crohn’s Disease. These are:

Disease Severity

The extent and severity of inflammation in the digestive tract play a crucial role in determining how long you can live with Crohn’s Disease. Mild to moderate cases of Crohn’s Disease, or cases with less aggressive to more persistent symptoms, generally have a better long-term prognosis than severe cases. 

This is due to the increased risk of serious complications like bowel obstruction, malnutrition, and systemic inflammation affecting other organs. Additionally, the persistent severe inflammation and the need for aggressive treatments can lead to secondary conditions, such as infections or cardiovascular disease, further impacting overall health and longevity.

Timely diagnosis and effective management can help prevent the progression of the disease to a more severe state.

Body’s Response To Treatment 

The variability in how individuals respond to treatments for Crohn’s Disease can profoundly impact their long-term health outcomes and lifespan. Patients who respond well to treatment may experience prolonged periods of remission, fewer complications, and a better quality of life, contributing to a longer lifespan. 

On the other hand, patients with a poor response to treatment may suffer from persistent, active disease and frequent flare-ups, leading to ongoing inflammation, more severe intestinal damage, and a higher risk of serious complications like strictures, fistulas, or even colorectal cancer. 

These complications can mean more aggressive treatments, which could carry their own risks and can further impact overall health and lifespan. 

Complications

It’s important to note that Crohn’s Disease can still lead to complications, particularly if left untreated or poorly managed. Here are some of the complications that have a significant impact on an individual’s lifespan. 

  • Malnutrition: Chronic inflammation in the digestive tract can lead to malabsorption of essential nutrients. Malnutrition can result in weight loss, weakness, and vitamin deficiencies, which can affect overall health and vitality.
  • Infections: Individuals with Crohn’s Disease may have a higher risk of developing infections, particularly if they are taking immunosuppressive medications to manage their condition. Serious infections, such as Tuberculosis (TB) and Septicemia, can be life-threatening if not treated promptly.
  • Bowel Obstruction: The inflammation and scarring associated with Crohn’s Disease can lead to bowel obstructions. These blockages can cause severe pain, vomiting, and dehydration. In some cases, emergency surgery, such as open and laparoscopic surgery, may be necessary to relieve the obstruction.
  • Fistulas: Crohn’s Disease can cause abnormal connections (fistulas) to form between different parts of the digestive tract and between the digestive tract and other organs. Fistulas can lead to complications such as abscesses and sepsis if not managed effectively through Biologic Therapies or Fistulotomy.
  • Cancer: Individuals with long-standing Crohn’s Disease have a slightly higher risk of developing colorectal cancer. Regular surveillance and colonoscopies are recommended to detect any precancerous changes or malignancies at an early and treatable stage.

Age And Gender

In a study by published in the Canadian Medical Association Journal, it was found that the death age for people with Crohn’s Disease and other inflammatory bowel diseases is 78.5 for males and 78.4 years for females.

Sadly, the life expectancy of a child with Crohn’s Disease is shorter. Researchers at Sweden’s Karolinska Institutet reveal that children who develop inflammatory bowel diseases below 18 years of age are at higher risk of mortality both during childhood and into adulthood. They have a mortality rate of three to five times higher than those without IBD. 


Crohn’s Disease Diagnosis

Doctor consulting a patient about Crohn's disease

Early detection is paramount in effectively managing Crohn’s Disease, as it allows for timely intervention to control inflammation, prevent complications, and improve the patient’s quality of life. A prompt diagnosis can also positively impact life expectancy. 

To confirm the presence of Crohn’s Disease, healthcare providers utilise a combination of medical history assessments, physical examinations, and various diagnostic tests.

  • Medical History: In the diagnostic process, medical history serves as a foundation, enabling healthcare professionals to gain insights into the patient’s symptoms, family history, and risk factors. 
  • Physical examinations: These tests provide additional information, including signs of abdominal tenderness, swelling, or other physical manifestations of the Disease.
  • Endoscopy: This involves procedures like a colonoscopy and an upper endoscopy, allowing for direct visualisation of the gastrointestinal tract. Biopsies can be taken during these tests to confirm inflammation characteristic of Crohn’s Disease.
  • Imaging: Magnetic Resonance Imaging (MRI) and Computed Tomography Scans (CT scans) provide detailed images of the digestive tract, helping identify affected areas and evaluate the extent of inflammation.
  • Blood Tests: Blood tests are essential because they can reveal signs of inflammation, anaemia, or nutritional deficiencies often associated with Crohn’s Disease.
  • Stool Tests: Analysing stool samples can help identify infections or other conditions that may mimic Crohn’s Disease symptoms.
  • Biomarker Testing: Certain biomarkers, such as C-reactive protein (CRP) and faecal calprotectin, can be measured to assess disease activity and response to treatment.

A definitive diagnosis of Crohn’s Disease is typically based on a combination of these assessments, enabling healthcare providers to tailor treatment plans to the individual’s specific needs.


Crohn’s Disease Pain Management

Assorted tablets and capsules used for treatment

While Crohn’s Disease can impact one’s health and quality of life, significant advances in medical research and treatment options have substantially improved the lives of many individuals with Crohn’s disease.

Pain management strategies often involve a multi-faceted approach, considering both medication and lifestyle modifications.

  • Acetaminophen (Tylenol): Acetaminophen is often prescribed for pain relief as it does not typically exacerbate inflammation in the gastrointestinal tract. However, it may not be as effective for severe pain.
  • Antispasmodic Medications: Antispasmodic drugs like dicyclomine or hyoscyamine can help relieve abdominal cramping and spasms.
  • Opioid Medications: Opioids, like codeine or tramadol, may be prescribed for severe pain in Crohn’s Disease for short-term use.
  • Corticosteroids: Corticosteroids, such as prednisone, may be used during disease flares to reduce inflammation and alleviate symptoms, including pain. They are not a long-term solution due to potential side effects.
  • Biologic Therapies: Biologic drugs, like anti-TNF agents (e.g., infliximab, adalimumab), work by targeting specific proteins in the immune system. They can help induce and maintain remission in Crohn’s Disease, which, in turn, can reduce pain and discomfort.
  • Immunomodulators: Medications like azathioprine or methotrexate may be prescribed to modulate the immune system and reduce inflammation in the gut, which can alleviate pain in Crohn’s Disease.
  • Lifestyle modifications: Changing the patient’s lifestyle can also help with pain management. Adopting a well-balanced diet that avoids trigger foods, regular exercise, and keeping a healthy mental state can alleviate symptoms and enhance overall well-being.


Conclusion About Crohn’s Disease Lifespan

It’s essential to clarify that Crohn’s Disease itself is generally not fatal. While it’s a chronic condition that requires ongoing management, it is not an immediate death sentence. Early detection is vital for effective pain management and improved life expectancy. 

For individuals seeking diagnostic tests to evaluate potential inflammatory bowel disease (IBD) or related gastrointestinal concerns, schedule an appointment at Advanced Colorectal And General Surgery. 

We offer a comprehensive range of diagnostic procedures, including colonoscopy and other advanced tests, to thoroughly assess your gastrointestinal health and guide you towards appropriate treatment options.


Frequently Asked Questions About Crohn’s Disease Lifespan

How Often Should Individuals With Crohn’s Disease Undergo Medical Check-Ups?

Regular follow-up appointments are essential, and the frequency depends on individual needs and disease activity.

What Support And Resources Are Available For Individuals And Families Coping With The Challenges Of Crohn’s Disease?

Support groups, patient advocacy organisations, and healthcare professionals can provide valuable support and resources.

Can Crohn’s Disease Go Into Remission, And If So, How Does This Affect Life Expectancy?

Yes, Crohn’s Disease can go into remission with appropriate treatment. During remission, the disease is less active, and individuals often experience improved quality of life, potentially extending their life expectancy.

What Foods Are Recommended For People With Crohn’s Disease?

Consuming low-fibre foods, lean proteins, cooked and peeled vegetables, ripe and peeled fruits, and dairy alternatives is generally advisable if lactose intolerant. Foods rich in omega-3 fatty acids and probiotic-rich foods like yoghurt can be beneficial.

Ulcerative Colitis: How Much Blood Is Too Much To Cause Concern?

Hand reaching for toilet paper

Ulcerative Colitis is a chronic inflammatory bowel disease (IBD) that affects millions of people worldwide. Characterised by the inflammation and ulceration of the colon’s inner lining, this condition often brings along a host of uncomfortable and debilitating symptoms, including blood in the stools. 

While this symptom is common among individuals with Ulcerative Colitis, how much blood is too much? Determining when it becomes a cause for concern can be challenging.

This article sheds light on the issue of blood in stools among Ulcerative Colitis patients. It explores why this symptom occurs, how to assess its severity, and most importantly, when it warrants medical attention. 


When To Be Concerned About Blood In Stool 

Ulcerative Colitis primarily affects the large intestine or colon. This chronic condition happens when there is an inflammation and a formation of ulcers (open sores) on the inner lining of the colon. Unlike Crohn’s disease, Ulcerative Colitis is confined to the colon and rectum.

Ulcerative Colitis can manifest with a range of symptoms, including

  • Diarrhoea, often with blood or mucus
  • Abdominal pain and cramping
  • Urgent need to have a bowel movement
  • Fatigue
  • Unexplained weight loss
  • Reduced appetite
  • Rectal bleeding

While rectal bleeding is a common occurrence among UC patients, it should not be overlooked. Patients must be attentive to and monitor the presence of blood in their stool, as excessive bleeding can pose significant health risks. Certain warning signs and red flags should prompt immediate concern and action.

Frequent Bowel Movement And Blood In Stool: A mild flare-up may result in several daily bowel movements with intermittent blood in the stool. In more severe flare-ups, individuals may experience six or more bowel movements per day, with blood consistently present.

The copious amount of blood in your stool is definitely a concern. If you notice a significant increase in the amount of blood in your stool or if you experience continuous or heavy bleeding, it is essential to contact your healthcare provider immediately. 

Signs Of Excessive Bleeding: You should also be aware of signs that suggest excessive bleeding, such as lightheadedness, dizziness, or weakness. Profuse or uncontrolled bleeding, especially if accompanied by symptoms like fainting, should be taken seriously and require immediate medical attention.

Severe abdominal pain: Intense abdominal pain, particularly if it is persistent or accompanied by bloating and distension, requires prompt evaluation.

Paleness: If you notice a marked paleness of your skin or experience symptoms of anaemia, such as persistent weakness and fatigue, it may indicate significant blood loss.

High fever: A high fever, especially if associated with chills, may suggest an infection or a complication of Ulcerative Colitis that requires immediate attention.

Change in mental status: Confusion, disorientation, or altered mental status should be taken seriously and investigated promptly.

Change in Symptoms: Pay attention to changes in your overall health and other UC symptoms. If you experience a decline in well-being, unexplained weight loss, or other new symptoms alongside rectal bleeding, it may warrant further evaluation.


Why Does Ulcerative Colitis Cause Blood In Stools?

Among the symptoms commonly associated with Ulcerative Colitis, rectal bleeding or blood in stools stands out as a significant and sometimes troublesome sign. This occurrence is intimately linked to the intricate pathophysiology of the disease.

The inflammation and ulceration in the colon can directly impact the delicate blood vessels residing within the colon’s tissues. When inflammation takes hold, it can weaken these blood vessels, which is why they are more susceptible to rupture.

As a result, even minor trauma or irritation to the colon’s lining can prompt these small blood vessels to break, leading to the leakage of blood into the intestinal contents. Consequently, the blood mixes with the stool as it traverses the colon, causing rectal bleeding.


Types Of Bleeding Associated With Ulcerative Colitis

Blood in stools can manifest in various ways for individuals with Ulcerative Colitis. They are classified into three different types of bleeding, including:

Gross Hematochezia

Gross Hematochezia refers to the noticeable and visible presence of bright red blood in the stool. The blood is usually vivid red in colour and is easily seen in the stool or on toilet paper after a bowel movement. 

It is often alarming and can be a cause for immediate concern because it is easily visible, indicating active and significant bleeding from the lower gastrointestinal tract.

The duration of gross hematochezia can vary. It may be intermittent, occurring during flare-ups, or it may be persistent in cases of severe bleeding.

Occult Bleeding

Occult bleeding is less apparent, as it involves the presence of blood in stools that may not be visually noticeable. The blood is typically not bright red but may be darker in colour or even black (melena). The bleeding can be intermittent and subtle.

Occult bleeding is often detected through specialised tests like faecal occult blood tests (FOBT) or faecal immunochemical tests (FIT), which can detect small amounts of blood not visible to the naked eye.

Mucosal Bleeding

In some cases, the bleeding may be limited to the colon’s mucosal layer. This type of bleeding may result in mucus-coated stools with streaks of blood. The blood may mix with mucus, making it appear less obvious than gross hematochezia.

Mucosal bleeding can be chronic and may persist over time, necessitating ongoing management and treatment to control inflammation. 


Monitoring Blood In The Stool For UC Patients

Planner with tablets for tracking ulcerative colitis medication

There isn’t a universally defined “normal” level of rectal bleeding in UC patients because it can vary widely. It’s important to keep track of your symptoms and let your healthcare provider know. They can help you figure out the best treatment based on your situation.

Individuals can use a simple scale to describe the amount of blood, ranging from minimal spotting to significant bleeding. This self-assessment can aid in monitoring changes in bleeding over time. While it may not replace a medical evaluation, it can provide valuable information.

  • Keep a Symptom Journal: Maintain a daily or weekly journal where you record your symptoms, including details about rectal bleeding. Note the frequency, consistency, and colour of blood in your stools. Be as specific as possible to help your healthcare provider understand your symptoms accurately.
  • Use the Bristol Stool Chart: This chart categorises stool types from 1 to 7, with 1 being very hard stools and seven being entirely liquid. Note where your stools fall on this scale and whether they are accompanied by blood. This can provide valuable information about changes in your bowel habits.
  • Measure Blood Loss: If you notice blood in your stools, you can try to estimate the amount. For example, you might describe it as “a few drops,” “streaks,” or “a noticeable amount.” This can help you gauge the severity of bleeding over time.
  • Monitor Other Symptoms: Alongside rectal bleeding, keep track of other UC symptoms such as abdominal pain, diarrhoea, fatigue, or changes in appetite. Understanding how these symptoms correlate with rectal bleeding can provide a more comprehensive picture of your condition.
  • Consult Your Healthcare Provider: Share your symptom journal with your doctor during regular check-ups or when you notice significant changes in your condition. Your healthcare provider can use this information to adjust your treatment plan and ensure your UC is well-managed.


Managing UC-Associated Rectal Bleeding

Person with highlighted pain in the large intestine

Rectal bleeding is common among individuals with UC, but it’s not necessarily a severe symptom for everyone. There is no cure yet for this condition. 

Fortunately, there are ways to manage its symptoms and reduce or stop rectal bleeding. This is necessary because left untreated, it increases the risk of developing colorectal cancer. 

To address excessive rectal bleeding in UC, doctors recommend a combination of medications and therapies tailored to the individual’s condition and the severity of their symptoms. 

Aminosalicylates: These anti-inflammatory drugs, such as mesalamine, help manage UC. They work by reducing inflammation in the colon’s lining, potentially alleviating rectal bleeding. Aminosalicylates can be administered orally or as rectal formulations, such as suppositories or enemas, for more targeted treatment.

Corticosteroids: In cases of more severe UC or during flare-ups, corticosteroids like prednisone may be prescribed. These medications are potent anti-inflammatories and are used to suppress inflammation quickly. 

Immunosuppressants: Medications like azathioprine or 6-mercaptopurine modulate the immune response. They can be effective in managing UC by reducing inflammation and preventing immune-related damage to the colon. These drugs are often used when aminosalicylates are ineffective or for maintaining remission.

Biologics: Biologic agents, such as infliximab or adalimumab, are advanced treatments that target specific proteins involved in the inflammatory process. Biologics are typically prescribed to patients with moderate to severe UC cases who do not respond to other treatments. They can be highly effective in managing UC symptoms and promoting remission.

Therapy: In addition to medications, certain therapies can directly address rectal bleeding in UC. For example, mesalamine enemas or suppositories deliver the medication directly to the rectum and lower colon, providing targeted relief from inflammation and bleeding in this area. These therapies are particularly useful in cases where rectal involvement is prominent.

Surgery: In severe cases of UC or when medications prove ineffective in controlling symptoms and preventing complications, surgery may be necessary. Doctors may recommend the removal of the colon (colectomy), with or without the creation of an ileal pouch-anal anastomosis (IPAA). Surgery can provide a long-term solution for managing UC but involves significant lifestyle adjustments and potential changes in bowel function.

Colonoscopy: Colonoscopy is a diagnostic procedure that can be performed to evaluate various gastrointestinal conditions, including rectal bleeding. It allows healthcare providers to visualise the colon and rectum directly to look for abnormalities, such as inflamed tissue, ulcers, polyps, or tumours that may be responsible for the bleeding.

One of the essential purposes of colonoscopy in cases of rectal bleeding is to screen for colorectal cancer. Colorectal cancer can cause rectal bleeding, and early detection through colonoscopy is crucial for successful treatment and improved outcomes.


Conclusion About UC-Associated Rectal Bleeding 

While rectal bleeding is a common symptom of UC, the level of concern depends on factors such as frequency, severity, and associated symptoms. Monitoring changes and discussing them with your healthcare provider is essential to determine their significance. 

It’s essential to remember that UC is a chronic condition often requiring ongoing treatment and monitoring. With the right approach, including medications, dietary modifications, and lifestyle adjustments, individuals with UC can achieve symptom relief, maintain remission, and enjoy an improved quality of life.

It’s important for people with UC to consult with reputable healthcare professionals like Dr. QM Leong. Regular consultations with experts can greatly improve the management of Ulcerative Colitis, enhance quality of life, and lower the risk of complications.

Book a consultation today!


Frequently Asked Questions About UC-Associated Rectal Bleeding

Can Diet Changes Help Manage Rectal Bleeding In Ulcerative Colitis?

Yes, dietary modifications can be beneficial for some individuals. Avoiding trigger foods and consuming a balanced diet may help reduce symptoms, including rectal bleeding.

Are There Natural Remedies For Addressing Bleeding In Ulcerative Colitis?

While some people find relief from natural remedies like aloe vera or curcumin supplements, it’s essential to consult with a healthcare provider before trying any alternative therapies.

Can Stress Exacerbate Rectal Bleeding In UC?

Stress can potentially worsen UC symptoms, including rectal bleeding, in some individuals. Stress management techniques and lifestyle adjustments may help mitigate its impact.

How Often Should Patients Undergo Colonoscopy For Surveillance?

The frequency of colonoscopy surveillance for UC patients varies based on disease severity and duration. Gastroenterologists typically recommend regular colonoscopies to monitor for complications and assess disease activity.

Is It Anal Fissure Or Haemorrhoid? 4 Key Differences

Person on a toilet with toilet paper, a sign of anal bleeding

Anal fissures and haemorrhoids are two common conditions that affect the anorectal region, causing discomfort and concern for many individuals. Though they share many similarities, such as their location and some symptoms, they have distinct causes, symptoms, and treatments, particularly when looking at what causes anal fissures and how they are typically managed in Singapore.

This article explains the differences between anal fissures and haemorrhoids and the best way to manage and treat each condition. 

What Is An Anal Fissure?

An anal fissure is a small, linear tear or cut in the mucosa of the anal canal. These tears typically result from the stretching of the anal mucosa beyond its capability, often due to passing large or hard stools or other forms of trauma such as childbirth or anal intercourse. 

This condition is characterised by severe pain and bleeding, especially during and shortly after bowel movements, which explains why anal fissures can cause bleeding during bowel movements.

Symptoms:

  • Sharp, intense pain during bowel movements, sometimes lasting hours after.
  • Bright red bleeding visible on toilet paper or stool.
  • A visible tear or cut in the skin around the anus.

Risk Factors:

  • Chronic constipation or diarrhoea: Repeated straining and prolonged irritation can lead to fissures.
  • Childbirth: Women are at higher risk postpartum due to the pressure and stretching during delivery.
  • Inflammatory bowel disease: Conditions like Crohn’s disease can make one more susceptible.
  • Tight anal sphincter muscles: Can reduce blood flow to the anorectal area, making the tissue more prone to tearing.
  • Age: Infants are prone to fissures, but they can occur at any age.

What Are Haemorrhoids?

Also called piles, haemorrhoids are swollen veins found in the rectal area. They can develop inside the rectum (internal haemorrhoids) or under the skin around the anus (external haemorrhoids). 

Haemorrhoids are primarily caused by increased pressure in the lower rectum because of straining during bowel movements, prolonged sitting or standing, obesity, pregnancy, or a low-fibre diet.

Symptoms:

  • Itching or irritation in the anal region.
  • Pain and discomfort while sitting or during bowel movements.
  • Swelling around the anus.
  • Painless bleeding during bowel movements

Risk Factors:

  • Age: As people get older, the supporting tissues in the rectum and anus can stretch and weaken, leading to an increased risk of developing haemorrhoids.
  • History of Chronic constipation or diarrhoea: Straining during bowel movements is a primary cause of haemorrhoids.
  • Pregnancy: The weight of the foetus can cause haemorrhoidal vessels to enlarge, along with hormonal changes. Delivery also increases pressure in these vessels.
  • Prolonged sitting: Staying seated for long periods, especially on the toilet, can increase the pressure on the veins in the anus and rectum.
  • Obesity: Excess weight, particularly around the midsection, can increase pressure on the pelvic veins.
  • Diet: A low-fibre diet can lead to constipation, resulting in straining during bowel movements.

Distinguishing Between Haemorrhoids Vs Anal Fissures

When trying to distinguish between haemorrhoids vs anal fissures, consider the nature and location of the pain, the bleeding pattern, and any additional symptoms like itching or the presence of lumps. 

Here’s a deeper look into how to differentiate the two based on pain type, bleeding patterns, and other symptoms:

1. Appearance

  • Anal fissures: They are small tears that appear as linear or oval-shaped ulcers in the posterior midline of the anus. They can be hard to see without proper positioning and lighting. Rarely, they can be found anteriorly or on the sides.

    The fissure can look like a fresh, red tear or a chronic, deeper ulcer with defined or raised edges. Swelling and redness may occur in the surrounding tissue if the area is irritated or infected. A sentinel pile, a tag of skin at the distal end of the fissure, can also sometimes be observed.

  • Haemorrhoids: Internal haemorrhoids are not visible externally although they may prolapse and protrude outside the anal canal. External haemorrhoids appear as lumps or swelling around the anal rim and can be felt as bulges at the anal opening. Haemorrhoids can be body-coloured, slightly redder, or blueish if thrombosed.

2. Type of Pain

  • Anal Fissures: The pain associated with anal fissures is typically acute and intense. It occurs during bowel movements as the stool passes the tear, causing a sharp, searing pain that can be quite severe and may be accompanied by minimal bleeding.

    The pain might continue for several hours after defecation, often described as feeling like passing glass shards. Fissures can also cause a spasm of the anal sphincter, further intensifying the pain.

  • Haemorrhoids: In contrast, haemorrhoids generally cause a duller, throbbing pain, especially when they are external and become thrombosed or prolapsed.

    The discomfort might increase while sitting or during bowel movements but doesn’t usually reach the acute intensity of fissure pain. Internal haemorrhoids might not be painful unless they prolapse or become thrombosed.

Person holding their bottom with highlighted anal pain

3. Bleeding Patterns

  • Anal Fissures: Bleeding is a common symptom associated with anal fissures, particularly when understanding why anal fissures can cause bleeding during bowel movements. When an anal fissure occurs, the small tear or crack in the lining of the anus can result in bright red blood during or after a bowel movement. This bleeding is typically minimal, but it can be noticeable on toilet paper or in the toilet bowl.
  • Haemorrhoids: Haemorrhoids can also cause bright red bleeding, but the pattern might differ. Internal haemorrhoids often lead to painless bleeding that might be noticed as streaks on the stool or pooling in the toilet bowl. External haemorrhoids, especially when they rupture or are thrombosed, can bleed significantly and sometimes clotted blood may be noticed.

4. Itching And Discomfort

  • Anal fissures: Don’t typically cause itching but can lead to significant discomfort due to the spasm of the anal sphincter muscle. These spasms can result in sharp, stabbing, or burning pain during or after bowel movements, making it uncomfortable for individuals with anal fissures to pass stools. 
  • Haemorrhoids: They can often lead to itching and skin irritation around the anal area, mainly when they are external, and cause swelling and inflammation of the surrounding skin. 

What Happens If Anal Fissures Or Haemorrhoids Are Left  Untreated?

If left untreated, both anal fissures and haemorrhoids can lead to more serious complications, especially in cases involving how chronic anal fissures develop and why they may not heal on their own. Anal fissures can develop into chronic pain, deeper fissures, and increased risk of infection.

Individuals may start avoiding going to the bathroom due to the pain, leading to constipation or impacted stools, which can exacerbate the problem.

Similarly, if left untreated, haemorrhoids can cause various complications, such as anaemia, become thrombosed, prolapsed haemorrhoids, skin tags, and infection. 

Prolapsed haemorrhoids can stretch and bulge outside the anus, while thrombosed haemorrhoids can be very painful and may require surgical intervention. 

Additionally, external haemorrhoids that are left untreated can lead to excess, saggy skin around the anus, known as skin tags, which can cause hygiene issues and further irritation. 

Diagnosing Anal Fissure Vs Haemorrhoids

Doctor reviewing notes with a patient

The accurate diagnosis of anal fissures and haemorrhoids involves a physical examination and other procedures by a healthcare professional. Here’s how each condition is generally diagnosed:

Anal Fissures

  • Visual Inspection: A doctor will look for visible signs of a tear in the lining of the anal canal. This is often evident as a small cut or ulcer, usually located posteriorly in the midline.
  • Digital Rectal Exam (DRE): This might be avoided if there’s severe pain, as it can be quite uncomfortable.
  • Anoscopy: A small, lighted tube (anoscope) may be used to view the anal canal more clearly. However, this might not be possible in acute fissures due to pain.

Haemorrhoids

  • Physical Examination: External haemorrhoids can often be seen or felt as swollen lumps around the anus. Internal haemorrhoids may not be apparent until they prolapse.
  • Digital Rectal Exam (DRE): During DRE, the doctor may feel for abnormalities inside the rectum.
  • Anoscopy or Proctoscopy: These tools are often used to view internal haemorrhoids or other causes of bleeding within the rectum.

Treatment Of Anal Fissures And Haemorrhoids

The treatment for haemorrhoids and anal fissures involves both conservative measures and, if necessary, more invasive medical procedures, including non-surgical and medical options for managing anal fissures in Singapore. Here’s an overview of the typical treatment approaches:

Anal Fissures

The treatment goals for anal fissures aim to provide relief from symptoms, promote healing, and prevent the recurrence of the conditions. Options include:

  • Topical Creams: Nitroglycerin ointment or other topical creams are prescribed to help relax the muscle around the anus (the internal anal sphincter), improving blood flow to the area and facilitating healing.
  • Warm Baths: Sitting in a few inches of warm water (sitz baths) several times a day can relax the sphincter muscle and promote healing.
  • Dietary Changes: Doctors may suggest increasing fibre intake and fluid consumption to soften stools and reduce strain on the fissure.
  • Stool Softeners: These may be recommended to reduce straining during bowel movements.
  • Surgery: In some cases where conservative treatment fails, a surgical procedure known as lateral internal sphincterotomy may be performed, particularly in situations involving when surgery may be recommended for persistent anal fissures.

Haemorrhoids

These haemorrhoid treatments can help relieve symptoms like pain, itching, bleeding, and discomfort, reducing swelling and promoting healing of hemorrhoidal tissue, while also preventing recurrence and addressing complications when necessary. 

  • Over-the-counter Creams and Suppositories: These can reduce itching, pain, and swelling. They often contain ingredients like hydrocortisone or witch hazel.
  • Cold Packs: To reduce swelling and pain, ice or cold packs must be applied to the area regularly.
  • Sitz Baths: Just like with fissures, warm water baths can provide relief from itching and discomfort.
  • Dietary Changes: Increasing fibre intake can prevent constipation, reducing the strain and pressure on haemorrhoids.
  • Minimally Invasive Procedures: For persistent or severe haemorrhoids, a doctor may perform rubber band ligation, sclerotherapy, or infrared coagulation to reduce or eliminate haemorrhoids.
  • Surgery: In severe cases, haemorrhoidectomy (removal of haemorrhoid) or haemorrhoid stapling may be necessary.

When To Seek Medical Help

Anal fissures and haemorrhoids can sometimes resolve on their own, especially if they are mild and appropriate lifestyle modifications are made. However, the healing process and likelihood of self-resolution depend on several factors, including the severity of the condition, underlying causes, and individual health and diet. 

There are specific situations in which it’s advisable to seek medical help for either condition:

  • Persistent Symptoms: If you have symptoms of an anal fissure, such as pain, bleeding, or discomfort, and they persist for more than a few days despite self-care measures, it’s a good idea to consult a healthcare provider. If you have haemorrhoid symptoms (pain, itching, bleeding, or swelling) that persist for more than a week despite self-care measures, consult a healthcare provider.
  • Severe Symptoms: If the pain associated with the anal fissure is severe, does not improve with over-the-counter pain relief, or interferes significantly with your daily life, a medical evaluation is recommended. Meanwhile, severe pain, excessive bleeding, or prolapsed haemorrhoids (when internal haemorrhoids protrude through the anus) require medical evaluation.
  • Frequent Recurrence: If you have recurrent anal fissures or haemorrhoids, it may indicate the need for treatment approaches used for long-standing or recurrent anal fissures.
  • Signs of Infection: If you notice signs of infection around the anal fissure, such as increased pain, redness, swelling, or the presence of pus, prompt medical attention is necessary.
  • Concerns About Cancer: In rare cases, rectal bleeding can be a sign of colorectal cancer. If you have significant rectal bleeding or bleeding associated with other concerning symptoms (such as unexplained weight loss or changes in bowel habits), it’s essential to seek prompt medical attention.

In both cases, your healthcare provider can perform a thorough evaluation, confirm the diagnosis, and recommend appropriate treatments.

Conclusion About Anal Fissures Vs Haemorrhoids

Anal fissures and haemorrhoids are two different conditions with different treatments and symptoms. Learning more about these conditions can prevent future occurrences and treat any symptoms effectively, especially with a complete overview of anal fissure diagnosis and treatment options in Singapore.

Remember, when in doubt, seek professional medical advice to get the correct diagnosis and treatment plan. At Advanced Colorectal And General Surgery, your comfort and health are our priority. 

Our specialist is experienced in performing advanced surgical procedures related to the colon, rectum, and other general surgical conditions. We strive to provide the most effective and personalised treatment options to ensure the best possible outcomes for our patients. Book an appointment today!

Frequently Asked Questions About Anal Fissures Vs Haemorrhoids

Can I Still Poop If I Have Anal Fissures Or Haemorrhoids?

Yes, you can still poop with anal fissures or haemorrhoids, but it may be uncomfortable or painful. To ease discomfort, it’s important to keep stools soft and regular through a high-fibre diet, plenty of hydration, and possibly the use of stool softeners. 

How Long Do Anal Fissures And Haemorrhoids Typically Take To Heal?

Acute fissures may heal within a few weeks with proper care. Chronic fissures might take longer and require medical treatment. For haemorrhoids, the healing time can vary. Mild haemorrhoids may improve within a few days, while more severe cases might take a few weeks and could recur or require medical intervention.

Are Anal Fissures And Haemorrhoids More Common At A Certain Age?

Both conditions can occur at any age but are more commonly seen in adults due to factors like increased pressure from long-term sitting, dietary habits, and, in the case of haemorrhoids, ageing-related weakening of the tissues.

Can Anal Fissures And Haemorrhoids Occur Simultaneously?

Yes, it is possible to have both anal fissures and haemorrhoids at the same time. These conditions can share similar symptoms, and a healthcare provider can help differentiate between them.

Ulcerative Colitis Vs IBS Vs Crohn’s Disease: Distinguishing The Differences

Doctor holding a model of the digestive system

Ulcerative Colitis (UC), Crohn’s Disease, and Irritable Bowel Syndrome (IBS) are all gastrointestinal conditions, but they are distinct and have different underlying causes. While they can share some symptoms, they are not connected regarding causation or pathology.

Both Ulcerative Colitis and Crohn’s Disease are types of Inflammatory Bowel Diseases (IBD) characterised by chronic inflammation in the gastrointestinal tract. 

IBS, on the other hand, falls under the category of functional gastrointestinal disorders and does not involve inflammation. 

This article compares IBS vs Crohn’s Disease vs Ulcerative Colitis, exploring the differences between the three, overlapping symptoms, and treatment options.


What Is Ulcerative Colitis (UC)?

Ulcerative Colitis is a health condition affecting the large intestine, causing inflammation and ulcers in its inner lining. Unlike some other types of IBD, Ulcerative Colitis usually only affects the colon and rectum. This condition can cause continuous inflammation and damage to the lining of your colon, leading to various symptoms.

Common Symptoms Of UC

The severity and combination of symptoms can vary among individuals with UC. Also, during periods of active disease (flare-ups) and periods of remission, the symptoms may improve or resolve. Some of the common indicators of UC are:

  • Bloody diarrhoea
  • Abdominal pain and cramping in the lower abdomen
  • The urgency to have bowel movements
  • Weight loss because of poor absorption of nutrients
  • Fatigue resulting from chronic inflammation and anaemia

Causes And Risk Factors Of UC

The cause of UC is still unknown. However, researchers think it might involve a combination of genetic, environmental, and immune system factors. 

Individuals with a family history of UC are at higher risk due to genetics. Additionally, environmental factors such as diet, smoking, and exposure to certain infections may also contribute to the development of UC.


What Is Crohn’s Disease?

Crohn’s Disease is a distinct form of Inflammatory Bowel Disease that sets itself apart from UC in several ways. Unlike UC, Crohn’s Disease is characterised by chronic inflammation that can affect multiple layers of the digestive tract, including not only the innermost mucosa but also the submucosa and even the deeper tissues. 

Additionally, Crohn’s Disease can exhibit a “skip” pattern, meaning it can involve some portions of the digestive tract while leaving healthy tissue untouched in between the inflamed areas. This distinctive feature can result in a patchy distribution of inflammation throughout the gastrointestinal tract.

Common Symptoms Of Crohn’s Disease

The symptoms of Crohn’s Disease can vary widely among individuals. They may come and go, and periods of remission can be interrupted by flare-ups.

  • Abdominal pain and cramping often in the lower right abdomen
  • Diarrhoea: Sometimes bloody
  • Fatigue and weight loss because of malabsorption of nutrients
  • Fistulas and abscesses or abnormal connections or pockets that may form in the digestive tract
  • Strictures: Narrowed areas of the bowel

Causes And Risk Factors Of Crohn’s Disease

Crohn’s Disease, like UC, has an unknown exact cause, but it is believed to stem from genetic predisposition, immune system factors, and environmental factors. A family history of Crohn’s disease and environmental factors like diet, smoking, and microbial triggers increase the risk of developing the condition.


What Is Irritable Bowel Syndrome (IBS)?

Irritable Bowel Syndrome (IBS) is classified as a functional gastrointestinal disorder, a medical term used to describe a group of conditions or disorders that primarily involve disturbances in the way the digestive system works rather than physical damage or visible abnormalities.

Unlike UC and Crohn’s Disease, IBS does not involve inflammation or structural damage to the digestive tract. Instead, it is characterised by abnormal gut motility and sensitivity, leading to a range of digestive symptoms.

Common Symptoms Of IBS

IBS symptoms can be diverse. Certain foods, stress, or hormonal changes may trigger or worsen these symptoms.

  • Abdominal pain or discomfort
  • Altered bowel habits: diarrhoea, constipation, or alternating between both (IBS-D, IBS-C, or IBS-M)
  • Bloating and gas: Due to abnormal gas handling by the gut
  • Mucus in stool: Without blood
  • Some people experience back pain

Causes And Risk Factors Of IBS

IBS is a complex and multifactorial condition which can be triggered by altered gut-brain communication, diet, and psychological factors. Stress, infections, and changes in gut microbiota can also exacerbate IBS symptoms. This condition can occur at any age but usually begins in early adulthood.


Common Gastrointestinal Symptoms Shared By UC, Crohn’s Disease, And IBS

Person holding their abdomen with cramping pain

Overlapping symptoms pose challenges in diagnosis and may lead to confusion among patients and healthcare professionals. Based on the information mentioned, the following are some of the common gastrointestinal symptoms the three conditions share: 

Abdominal Pain and Discomfort: All three conditions can cause abdominal pain and discomfort at varying degrees. While the location and nature of pain may differ, this shared symptom can make it difficult to distinguish among them.

Diarrhoea: Diarrhoea is a common symptom in both UC and Crohn’s Disease due to inflammation and disrupted bowel function. IBS, particularly the subtype IBS-D (IBS with diarrhoea), is also characterised by recurrent episodes of diarrhoea.

Bloating and Gas: Bloating and excessive gas can occur in all three conditions. It may result from altered gut motility, fermentation of undigested food, or bacterial overgrowth.


Clinical And Pathological Differences

Healthcare professionals consider key factors to differentiate Ulcerative Colitis (UC), Crohn’s Disease, and Irritable Bowel Syndrome (IBS).

Affected Areas Of The Digestive Tract

  • UC primarily affects the colon and rectum, with continuous inflammation and ulceration limited to this region.
  • Crohn’s Disease can impact any part of the digestive tract, potentially involving the mouth, oesophagus, stomach, small intestine, and large intestine. It may also exhibit “skip” lesions, leaving healthy tissue between inflamed areas.
  • IBS does not involve structural damage or inflammation in the digestive tract but rather functional abnormalities in gut motility and sensitivity.

Inflammation Patterns

  • UC is characterised by continuous, uniform inflammation and ulceration in the colon’s mucosal lining.
  • In Crohn’s Disease, inflammation can be patchy and transmural (affecting multiple layers) and may skip segments, resulting in a “cobblestone” appearance and a higher risk of complications.
  • IBS lacks inflammation; its symptoms primarily stem from abnormal gut contractions and heightened sensitivity.

Histological Differences

  • Biopsy samples from patients with ulcerative colitis typically exhibit inflammation confined to the colon’s mucosal layer.
  • In Crohn’s Disease, biopsy samples may reveal deeper inflammation that involves the submucosa and other layers of the digestive tract.
  • IBS biopsies do not show signs of inflammation but may display nonspecific changes in some cases.


How Different Tests Help Diagnose UC, IBS, And Crohn’s Disease?

Doctor preparing an endoscope for a procedure

Individuals experiencing gastrointestinal symptoms should seek a comprehensive medical evaluation to ensure an accurate diagnosis and appropriate treatment plan. 

A healthcare professional, typically a gastroenterologist, will use the combination of clinical findings and diagnostic tests to differentiate ulcerative colitis, IBS and Crohn’s disease, ultimately guiding the most suitable management approach.

Endoscopy And Colonoscopy Findings

During a colonoscopy procedure for UC, it is common to find inflamed mucosa with ulcers in the colon and rectum that are continuous. 

However, in Crohn’s Disease, a colonoscopy may show deeper ulcerations, skip lesions and a more patchy appearance. 

On the other hand, IBS usually appears normal during endoscopy and colonoscopy, with no signs of inflammation or structural abnormalities.

Imaging Studies

Imaging techniques like MRI or CT scans can help differentiate Crohn’s from UC by highlighting the extent of bowel involvement and complications like strictures or fistulas. 

In IBS, imaging studies are usually unremarkable, as there are no structural changes in the digestive tract.

Blood Tests And Stool Samples

In cases of IBD, blood tests for inflammatory markers like C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) are often elevated. 

However, in IBS, these markers are typically not elevated. Additionally, stool samples can also be helpful in detecting the presence of blood or inflammation markers. These markers are more likely present in IBD, such as UC and Crohn’s, but not in IBS.


Treatment Approaches

Once a healthcare professional has accurately diagnosed Ulcerative Colitis, Crohn’s Disease, or IBS, the next crucial step is to develop a treatment plan tailored to the specific condition. Each of these gastrointestinal disorders requires a different approach to management.

Management Strategies For Ulcerative Colitis 

Medications: Medications are essential in UC management. They can include anti-inflammatory drugs (e.g., 5-aminosalicylates), immunosuppressants, corticosteroids, and biologics. These medications aim to reduce inflammation, control symptoms, and induce and maintain remission.

Dietary Considerations: Some individuals with UC may benefit from dietary modifications, such as a low-residue diet during flare-ups. However, dietary changes should be discussed with a healthcare provider or dietitian to ensure they meet nutritional needs.

Surgery as a Last Resort: Doctors recommend surgery in severe cases of UC or when medical treatments are ineffective. Surgery may involve the removal of the colon and rectum (proctocolectomy) with the creation of an ileal pouch-anal anastomosis (IPAA) or a permanent ileostomy.

Management Strategies For Crohn’s Disease

Medications Targeting Inflammation: Medications for Crohn’s aim to reduce inflammation and suppress the immune system. These can include aminosalicylates, corticosteroids, immunomodulators, and biologics. The choice of medication depends on the location and severity of the disease.

Nutritional Therapy: Nutritional interventions, such as enteral nutrition or exclusive enteral nutrition (EEN), can help induce remission, particularly in children with Crohn’s. Specialised diets may also be used in some cases.

Surgical Options: Surgery may be necessary for complications like strictures, fistulas, or abscesses. Surgical procedures can involve removing damaged sections of the intestine, but surgery does not cure Crohn’s Disease, and symptoms can return.

Management Strategies For Irritable Bowel Syndrome (IBS)

Dietary Modifications: Identifying and avoiding trigger foods is a common approach for managing IBS. The low FODMAP diet, for example, has shown promise in reducing symptoms for some individuals.

Medications for Symptom Relief: Depending on the predominant symptom (diarrhoea, constipation, or abdominal pain), medications such as antispasmodics, laxatives, or anti-diarrheal drugs may be prescribed for symptom relief.

Psychological Therapies: Psychological factors, such as stress and anxiety, can worsen IBS symptoms. Cognitive-behavioural therapy (CBT), relaxation techniques, and mindfulness-based therapies may help manage stress and improve IBS symptoms.

Lifestyle Changes: Keeping a healthy lifestyle by exercising regularly, getting enough sleep, and practising stress management techniques can significantly reduce IBS symptoms.


Conclusion About Ulcerative Colitis Vs IBS Vs Crohn’s Disease

Ulcerative Colitis and Crohn’s Disease are both types of Inflammatory Bowel Disease (IBD), while IBS is a functional gastrointestinal disorder. UC targets the colon and rectum, while Crohn’s Disease affects a broader area of the digestive tract. 

Both IBD variants cause chronic discomfort and complications due to inflammation. In contrast, IBS is characterised by irregular gut motility and heightened sensitivity without inflammation or structural damage. 

The key takeaway is that accurate diagnosis is essential for selecting the most appropriate treatment plan. When developing a tailored approach, healthcare professionals will consider the individual’s specific symptoms, disease severity, and response to previous treatments. 

If you’ve been experiencing any issues with your gastrointestinal system, it’s important to get the right medical advice and treatment. Seeking the help of an experienced healthcare professional like Dr Leong Quor Meng can be incredibly beneficial. 

With his expertise and guidance, you can get the care and support you need to improve your overall health and well-being. Contact us today!


Frequently Asked Questions About Ulcerative Colitis Vs IBS Vs Crohn’s Disease

Are There Any Specific Foods Triggering Symptoms in All Three Conditions: UC, IBS, and Crohn’s Disease?

While there are no universally triggering foods for all three conditions, some individuals may find that certain common culprits like spicy foods, caffeine, alcohol, and high-fat or high-fibre foods can exacerbate symptoms in UC, IBS, and Crohn’s. However, specific food triggers can vary widely from person to person, making it essential to identify individual dietary sensitivities.

Can Stress Cause The Development Of Any Of These Conditions, Or Does It Only Worsen Symptoms?

Stress is not considered a direct cause of UC, Crohn’s Disease, or IBS. However, stress can exacerbate symptoms and trigger flare-ups in individuals who already have these conditions. Stress management and psychological support are important components of managing these gastrointestinal disorders effectively.

Is There A Cure For UC, Crohn’s Disease, Or Ibs?

Currently, there is no cure for UC, Crohn’s Disease, or IBS. However, with appropriate medical management, lifestyle adjustments, and dietary modifications, many individuals can achieve symptom relief, remission, and an improved quality of life.

Can UC Turn Into Crohn’s Disease Or Vice Versa Over Time?

While both UC and Crohn’s are forms of Inflammatory Bowel Disease (IBD), it is uncommon for one condition to transform into the other. However, a subset of patients may exhibit features of both conditions, known as “indeterminate colitis.” These cases can pose diagnostic challenges and may require ongoing monitoring and tailored treatment.

Ulcerative Proctitis Vs Colitis: Symptoms, Causes, And Key Differences

Differences between proctitis and colitis

Among the various disorders that can affect the digestive system, ulcerative proctitis and ulcerative colitis are two distinct yet related conditions that are often confused.

In this article, we will delve into the world of these inflammatory bowel diseases (IBDs) and provide clarity on the key differences between ulcerative proctitis and ulcerative colitis. You’ll identify your symptoms and understand the different diagnoses and treatment options for each condition.


What Is Ulcerative Proctitis?

Ulcerative proctitis (UP) is an inflammatory bowel disease affecting only the rectum, the last part of the colon or large intestine. In this condition, inflammation is localised to the rectum and does not extend to other parts of the colon. 

The inflammation in ulcerative proctitis is characterised by the formation of ulcers on the inner lining of the rectum.

Symptoms And Common Indicators Of UP

  • Rectal Bleeding: One of the common symptoms of ulcerative proctitis is rectal bleeding. Blood in the stool or on toilet paper is a common occurrence and is typically attributed to the inflammation and ulceration of the rectal lining.
  • Frequent Urgency to Have a Bowel Movement: Ulcerative proctitis often leads to a strong and frequent urge to have a bowel movement. This urgency can be distressing and may result in multiple trips to the restroom throughout the day.
  • Passage of Bloody or Mucus-Filled Stools: Stools in ulcerative proctitis can contain blood or mucus. The presence of blood is a direct result of inflammation and ulceration in the rectum. Mucus may also be present due to the irritation and inflammation of the rectal lining.
  • Abdominal Cramps and Discomfort: Patients with ulcerative proctitis may experience abdominal cramps and discomfort. These symptoms can range from mild to severe and are often associated with inflammation in the rectum and lower part of the colon.
  • Feeling of Incomplete Evacuation: Some individuals with ulcerative proctitis may feel as though they have not fully evacuated their bowels after a bowel movement. This sensation can be frustrating and is often related to inflammation and the presence of mucus in the rectum.

Causes And Risk Factors Of UP

The causes and risk factors of ulcerative proctitis (UP) can vary, and it’s often a complex interplay of factors that contribute to the development and exacerbation of the condition. These include:

  • Abnormal Immune Response: Inflammatory bowel diseases (IBD), including ulcerative proctitis, are believed to originate from an abnormal immune response within the gastrointestinal tract. The immune system mistakenly attacks and inflames the lining of the rectum in UP, leading to the characteristic symptoms.
  • Family History: Genetics can play a significant role in the development of UP. Having a family history of IBD, including ulcerative proctitis, increases the risk of an individual developing the condition. Specific genes related to immune function and inflammation are associated with an increased susceptibility to IBD.
  • Infections: Infections, especially gastrointestinal infections, may trigger or contribute to the development of UP in some cases. These infections can potentially lead to an abnormal immune response or trigger inflammation in the rectal area.
  • Dietary Factors: While diet alone is not a direct cause of UP, certain dietary patterns and food intolerances may exacerbate symptoms in susceptible individuals. Some individuals may find that specific foods or dietary habits worsen their condition or trigger flare-ups.
  • Stress: Psychological stress is known to exacerbate symptoms of UP and other IBDs. Chronic stress can trigger or intensify inflammation in the gastrointestinal tract, leading to symptom aggravation.
  • Smoking: Smoking is considered a significant risk factor for UP and other forms of IBD. It is known to increase the risk of developing UP and can also worsen the course of the disease. Quitting smoking is often recommended as part of the management plan for UP.


What Is Ulcerative Colitis?

Ulcerative colitis (UC) is a type of inflammatory bowel disease that causes inflammation and sores in the colon, a part of the large intestine. It’s similar to another disease called ulcerative proctitis, but it affects a larger colon area. This condition can cause chronic inflammation and ulcers in the lining of the colon.

Some cases of ulcerative colitis develop from proctitis. The progression happens when proctitis is left untreated or if the inflammation gradually spreads from the rectum to the other parts of the colon.

Symptoms And Common Indicators Of UC

UC symptoms can be more extensive and severe than ulcerative proctitis. Patients often experience the following indicators:

  • Bloody Diarrhoea: One of the hallmark symptoms of UC is bloody diarrhoea. The inflammation and ulceration in the colon and rectum can lead to the passage of stools that contain blood or mucus.
  • Abdominal Pain and Cramping: UC often causes abdominal discomfort and cramping. These symptoms can range from mild to severe and are typically associated with the inflammation and irritation of the intestinal lining.
  • Weight Loss: Persistent diarrhoea, reduced appetite, and malabsorption of nutrients can lead to unintentional weight loss in UC patients. Maintaining a healthy weight can be challenging during active disease phases.
  • Fatigue and General Malaise: Chronic inflammation and the body’s immune response can lead to fatigue and a general feeling of being unwell (malaise). UC patients may experience low energy levels and a reduced sense of well-being.
  • Extraintestinal Symptoms: In addition to gastrointestinal symptoms, UC can also manifest with extraintestinal symptoms that affect other parts of the body. These may include joint pain (arthritis), skin rashes (dermatitis or erythema nodosum), and eye inflammation (uveitis or conjunctivitis).
  • Frequent Urgency to Have a Bowel Movement: UC patients often experience a frequent and urgent need to have a bowel movement, which can disrupt daily activities.
  • Feeling of Incomplete Evacuation: Similar to ulcerative proctitis, some individuals with UC may feel as though they have not fully evacuated their bowels after a bowel movement.

Causes And Risk Factors Of UC

The causes and risk factors of ulcerative colitis (UC) are multifactorial and involve a complex interplay of genetic, environmental, and immune factors. Here’s a breakdown of these causes and risk factors:

  • Genetic Factors: UC is believed to have a genetic component. Individuals with a family history of IBD, including UC, are at a higher risk of developing the condition. Specific genes related to the immune system and inflammation have been associated with an increased susceptibility to UC. However, having a genetic predisposition does not guarantee that an individual will develop the disease.
  • Environmental Triggers: While genetics play a role, environmental factors are also thought to contribute to the onset of UC. These factors can include dietary choices, exposure to infections, and other environmental elements. However, the precise environmental triggers are not fully understood and may vary from person to person.
  • Immune Dysregulation: UC is considered an autoimmune disease, where the body’s immune system mistakenly attacks its own intestinal lining. Immune dysregulation is a key factor in the development of UC, as the immune system becomes overly activated in the gastrointestinal tract, leading to chronic inflammation and damage.
  • Smoking: Smoking is associated with an increased risk of UC development, but paradoxically, it may have a protective effect against UP (ulcerative proctitis). However, the reasons for this difference are not fully understood, and the overall health risks associated with smoking outweigh any potential benefits related to UC.


4 Key Differences Between Ulcerative Proctitis Vs Colitis

Miniature figures beside a model of the colon

When it comes to distinguishing between ulcerative proctitis and ulcerative colitis, it’s essential to recognise the key differences that set these two conditions apart:

  • Location of Inflammation: One of the primary distinctions between the two is the location of inflammation. Ulcerative proctitis is localised to the rectum, whereas ulcerative colitis involves inflammation that extends throughout the colon. This distinction has significant implications for symptoms and treatment.
  • Extent of Inflammation: Proctitis is considered a milder form of inflammatory bowel disease because it affects a limited area. In contrast, ulcerative colitis often affects a larger portion of the colon, leading to a broader range of symptoms and potential complications.
  • Potential Complications: The limited scope of ulcerative proctitis reduces the likelihood of certain complications that are more common in ulcerative colitis. For instance, severe inflammation throughout the colon can lead to complications like colonic strictures, fistulas, or an increased risk of colorectal cancer. 
  • Disease Severity: The level of severity can vary in both proctitis and ulcerative colitis. In ulcerative colitis, it is described as mild to severe, depending on the extent and intensity of the inflammation. In contrast, ulcerative proctitis is often categorised as milder. The severity of the condition plays a critical role in determining the appropriate treatment approach.


Similarities And Overlapping Symptoms Of Proctitis And Colitis

While ulcerative proctitis and ulcerative colitis have distinct characteristics, there can be some overlap in symptoms, which can complicate the diagnosis process. Common overlapping symptoms include:

  • Rectal Bleeding: Both conditions can result in rectal bleeding, which may manifest as blood in the stool or on toilet paper. Rectal bleeding is a hallmark symptom of ulcerative proctitis but can also occur in ulcerative colitis.
  • Frequent Urgency: The urgent need to have a bowel movement is a shared symptom of both diseases. Individuals with either condition may experience a strong and sudden urge to use the restroom.
  • Abdominal Discomfort: Abdominal discomfort can be present in both conditions, including cramps and pain. This discomfort can vary in intensity and location.
  • Diarrhoea: Diarrhoea is a common symptom in both ulcerative proctitis and ulcerative colitis, although the severity and frequency can differ.
  • Mucus in Stool: The passage of mucus in stool is another sign both conditions share.
  • Weight Loss and Fatigue: These systemic symptoms may affect individuals with either condition, particularly when inflammation is more widespread in ulcerative colitis.


Diagnosing Ulcerative Proctitis Vs Ulcerative Colitis

Diagnosing ulcerative proctitis and ulcerative colitis involves a comprehensive evaluation by healthcare professionals or Gastroenterologists. Here’s an overview of the diagnostic process:

  • Medical History: A detailed medical history, including a discussion of symptoms and any family history of inflammatory bowel disease, is important for accurate diagnosis. 
  • Physical Exam: Doctors may also require a physical examination to assess the patient’s overall health.
  • Laboratory Tests: Blood tests can help identify signs of inflammation, anaemia, or nutritional deficiencies associated with both conditions. Increasing C-reactive protein (CRP) levels or erythrocyte sedimentation rate (ESR) may suggest active inflammation.
  • Stool Samples: Analysis of stool samples can help rule out infections and check signs of blood, mucus, or pathogens. Stool tests can provide valuable information to aid in diagnosis.
  • Colonoscopy: Colonoscopy is a crucial diagnostic tool for both ulcerative proctitis and ulcerative colitis. Using a flexible tube with a camera helps visualise the colon’s lining and identify areas of inflammation. Biopsies may be taken during the colonoscopy to confirm the diagnosis and rule out other conditions.
  • Flexible Sigmoidoscopy: In cases of suspected ulcerative proctitis, a flexible sigmoidoscopy may be performed to examine the rectum and lower part of the colon specifically. This procedure is less invasive than a full colonoscopy but can provide valuable diagnostic information.
  • Imaging Studies: In some instances, imaging studies such as CT scans or MRIs help evaluate the extent and severity of inflammation, especially in cases of ulcerative colitis.


Treatment Options For Ulcerative Colitis And Proctitis

Bottles of medication and tablets on a table

Treatment for ulcerative proctitis and ulcerative colitis is aimed at achieving symptom control, inducing and maintaining remission, and improving the patient’s quality of life. It depends on the severity of the condition and may include the following options:

Medications

  • Anti-Inflammatory Medications: Aminosalicylates, such as mesalamine, are often prescribed to reduce inflammation and symptoms in both ulcerative proctitis and ulcerative colitis.
  • Immunosuppressants: Immunosuppressive medications like azathioprine or methotrexate may be used to modulate the immune response and prevent inflammation.
  • Biologics: Biologic therapies, such as infliximab or adalimumab, target specific molecules in the immune system and can be effective in managing symptoms and inducing remission, especially in moderate to severe cases of ulcerative colitis.
  • Steroids: Corticosteroids may be prescribed for short-term use to rapidly reduce inflammation during flare-ups, but they are not suitable for long-term maintenance due to potential side effects.

Lifestyle Modifications

Making dietary changes can help some people deal with their symptoms. For example, avoiding certain trigger foods or adopting a low-residue diet during flare-ups can bring relief. 

Additionally, managing stress is essential, as it can worsen symptoms. Mindfulness, yoga, or counselling may be helpful techniques to reduce stress.

Colectomy Surgery

A colectomy is a medical procedure done to remove a portion or the entire colon. If medications fail, surgery may be needed for severe ulcerative colitis or life-threatening complications like bleeding, colon perforation, toxic megacolon, or developing colorectal cancer. Chronic symptoms like pain, diarrhoea, and weight loss can also be improved with surgery.

Treatment plans are highly individualised, and healthcare providers work closely with patients to tailor approaches to their specific needs and goals. Regular follow-up appointments and ongoing monitoring are important to ensure the treatment’s effectiveness and to adjust the management plan as needed. 

Ultimately, the goal is to provide patients with the best possible quality of life while managing their condition.


Conclusion Ulcerative Proctitis Vs Colitis

Ulcerative proctitis is localised to the rectum, resulting in symptoms such as rectal bleeding, urgency, and discomfort. On the other hand, ulcerative colitis involves inflammation throughout the colon, leading to a broader range of symptoms and potential complications.

If you or someone you know is experiencing gastrointestinal symptoms, we strongly encourage you to seek medical attention promptly. Early diagnosis and proper management are crucial for controlling symptoms, preventing complications, and maintaining a good quality of life.

We also recommend considering Advanced Colorectal and General Surgery as a trusted resource for diagnosis and treatment. With cutting-edge technology and a specialist surgeon in Singapore dedicated to digestive health, they can provide tailored advice and care that meets your unique needs. 

Book an appointment today to take the first step toward understanding and managing your gut health. Your well-being is our priority.


Frequently Asked Questions About Ulcerative Proctitis Vs Colitis

When Should I Seek Medical Attention If I Suspect I Have These Conditions?

If you experience symptoms such as rectal bleeding, persistent diarrhoea, abdominal pain, or unexplained weight loss, it’s essential to consult a doctor promptly for the correct diagnosis and treatment plan tailored to your specific needs.

Is There A Cure For Ulcerative Proctitis Or Ulcerative Colitis?

While there is no known cure for these conditions, they can often be managed effectively with medication and lifestyle changes to achieve symptom control and remission.

Are There Specific Dietary Recommendations For Individuals With Ulcerative Proctitis Or Ulcerative Colitis?

Dietary recommendations can vary from person to person. Some individuals may benefit from dietary modifications, such as a low-residue or low-FODMAP diet, while others may require no specific dietary changes. Consulting with a professional dietitian or healthcare provider can help determine the best approach.

Can Children Develop Ulcerative Proctitis Or Ulcerative Colitis?

Yes, children can develop these conditions. Paediatric gastroenterologists specialise in diagnosing and managing inflammatory bowel diseases in children.

5 Signs You Need A Colonoscopy Today 

Key signs that indicate a colonoscopy is needed

To maintain optimal health, understanding when to seek medical intervention is crucial. One such intervention is a colonoscopy, a diagnostic procedure allowing doctors to closely examine the inner lining of your colon and rectum.

This process gently guides a flexible tube equipped with a camera through the colon, providing real-time imagery to identify abnormalities.

This article aims to illuminate the gastrointestinal problems and other key signs you need a colonoscopy screening, vital step in detecting issues like colon cancer and ensuring gastrointestinal wellness.


1. Persistent Change In Bowel Habits

Regular bowel habits differ from person to person but generally involve a consistent pattern in stool frequency and appearance. A healthy digestive tract and bowel movements could range from three times a day to three times a week, depending on the individual.

Several factors can lead to alterations in bowel habits, ranging from diet and lifestyle changes to stress and infections. 

However, persistent changes, especially those lasting over a few weeks, could signal underlying health issues. Conditions such as bowel cancer, inflammatory bowel diseases like Crohn’s disease or ulcerative colitis, and irritable bowel syndrome (IBS) can manifest as changes in bowel habits.


2. Blood In Stool Or Rectal Bleeding

If you notice blood in the stool or rectal bleeding is a symptom that should always be taken seriously. Common causes include:

However, these symptoms can also indicate more severe conditions like bowel cancer or inflammatory bowel diseases.

Bloody stools offer clues about the source of bleeding. Bright red blood usually suggests bleeding from the lower colon or rectum, while darker blood or blood mixed within the stool indicates an issue higher in the colon. Other associated symptoms can include abdominal pain, a sensation of incomplete bowel evacuation, and changes in bowel habits.

A colonoscopy enables a comprehensive examination of the colon and rectum, helping identify the bleeding source. During the procedure, if any abnormal growths or areas of inflammation are detected, tissue samples can be taken for further analysis, aiding in the accurate diagnosis and effective management of the underlying condition.

Person holding their stomach with abdominal pain

3. Persistent Abdominal Discomfort or Pain

Abdominal discomfort or pain that persists over time can be a significant warning sign of potential gastrointestinal issues, including colon cancer. This pain may manifest as a constant ache, sharp pains, or general discomfort in the abdominal area. While many conditions can cause such symptoms, persistent pain should never be ignored.

A colonoscopy can play a crucial role in identifying the underlying cause of this pain. This diagnostic procedure allows doctors to visually examine the inner lining of your colon and rectum for abnormalities. 

Causes for abdominal pain might range from benign issues like irritable bowel syndrome (IBS) to more serious concerns such as colon polyps or bowel cancer.

The presence of colon polyps, which are growths on the inner lining of the colon, can sometimes lead to cancer if left unchecked. Through a colonoscopy, these polyps can be identified and often removed before they develop into cancer.


4. Unexplained Weight Loss

Experiencing unexplained weight loss can be alarming. This symptom, especially when accompanied by changes in bowel habits or rectal bleeding, should be taken seriously as it can be indicative of bowel cancer or other serious digestive disorders.

Weight loss might occur because a disease in the colon can affect the body’s ability to absorb nutrients properly. Additionally, certain gastrointestinal conditions can lead to a decreased appetite or a feeling of fullness after eating only a small amount of food, contributing further to weight loss.

When you undergo a colonoscopy, your doctor looks for signs that might explain this weight loss. They might find inflammation, blockages, or growths causing these symptoms. The procedure can also help in the detection of colon cancer, which is a significant concern behind unexplained weight loss.

Colon cancer, if caught early, can often be treated effectively. This is why recognising these symptoms and opting for a timely colonoscopy is crucial. The procedure helps diagnose the issue and sets the stage for the necessary treatment plan.

Person standing on a bathroom scale

5. Unexplained Anaemia (Low Red Blood Cell Count)

Anaemia, characterised by a lower than normal red blood cell count, can be a silent signal pointing towards underlying health issues, including colon cancer. It’s crucial to understand that while anaemia can be caused by various factors, such as nutritional deficiencies or chronic diseases, it can also be a sign of internal bleeding.

This internal bleeding could very well originate from the colon or rectal areas. When you experience symptoms such as fatigue, weakness, or paleness alongside unexplained anaemia, it’s important to consider the health of your gastrointestinal tract. A colonoscopy becomes a vital tool in such situations.

Family of three generations sitting together at home

Other Factors That Affect Your Need For A Colonoscopy

While the symptoms mentioned above are direct indicators suggesting the need for a colonoscopy, other factors might influence this decision.

The Right Age

Age is a significant factor in determining the necessity of a colonoscopy. Generally, individuals aged 50 and above are at a higher risk of developing colon cancer. 

Therefore, routine colonoscopies are often recommended for this age group. This proactive approach helps in the early detection and treatment of any potential issues, including precancerous polyps that could develop into bowel cancer.

Family History

Your family history plays a crucial role in assessing your risk for colon cancer. If you have a family history of colon or bowel cancer or a related condition, your doctor might recommend earlier or more frequent colonoscopies. Genetic factors can significantly increase your risk of developing these cancers.


Why Skipping A Colonoscopy Can Be Fatal

The importance of a colonoscopy cannot be overstated, especially regarding colon cancer screening. Colon cancer, if detected early, can often be treated effectively. 

However, if ignored, the condition can progress and become fatal. A colonoscopy allows doctors to search for, identify, and even remove polyps. These polyps, which are small growths, can develop into cancer over time when left alone.

Early removal of these polyps significantly reduces the risk of cancer.

Moreover, symptoms like rectal bleeding, abdominal pain, and changes in bowel habits often go unnoticed or are attributed to less serious conditions. This delay in diagnosis can lead to the cancer advancing to a more severe stage, making treatment more complicated and less likely to succeed.


Colonoscopy Alternatives

While colonoscopy is the gold standard for colorectal cancer screening and diagnosis, several alternative methods are available for those who cannot undergo this procedure or prefer different options. Here’s a brief overview of some common alternatives:

  1. Fecal Immunochemical Test (FIT): This non-invasive test detects hidden blood in the stool, which can be a sign of colon cancer. It’s usually done annually and requires no special preparation or dietary restrictions.
  2. Virtual Colonoscopy (CT Colonography): This imaging test uses CT scans to visually examine the colon. It requires the same bowel preparation as a regular colonoscopy but doesn’t involve sedation or inserting a scope into the colon. It’s usually recommended every 5 years.
  3. Double-Contrast Barium Enema (DCBE): This X-ray exam of the colon and rectum uses a barium solution and air to provide clear images of the lining of the colon. It’s less commonly used now but can be an option for some patients.

Each of these alternatives has its own pros and cons, and none is as comprehensive as a traditional colonoscopy. Therefore, it’s essential to discuss with your healthcare provider the best option for your individual health needs and risk factors.

Laboratory technician testing a sample

Conclusion On Signs You Need A Colonoscopy

A colonoscopy is a critical tool in the early detection and prevention of colon and bowel cancer. Recognising the signs that you may need a colonoscopy is crucial.

If you experience any of these symptoms, it’s essential to consult a healthcare professional promptly. Remember, early detection through a colonoscopy can save lives. Dr. QM Leong is an experienced colorectal surgeon in Singapore who is equipped to provide thorough evaluations and treatments. 

Schedule a consultation if you have any concerning changes in your gut health. Your well-being may depend on it.


Frequently Asked Questions On Signs You Need A Colonoscopy

How Often Should One Undergo A Colonoscopy? 

Typically, a colonoscopy is recommended every ten years starting at age 50. However, if polyps are found or if there are other risk factors, more frequent colonoscopies may be necessary.

Can A Colonoscopy Detect Conditions Other Than Colon Cancer? 

Yes, a colonoscopy can detect a variety of conditions apart from colon cancer, such as inflammatory bowel disease (IBD), diverticulosis, and polyps that could potentially turn into cancer.

Is There Any Preparation Required Before A Colonoscopy? 

Preparation typically involves a clear liquid diet for a day or two before the procedure and taking a bowel-cleaning solution to empty the colon.

Are There Any Risks Associated With A Colonoscopy? 

Colonoscopies are generally safe, but like any medical procedure, they carry risks, such as bleeding, perforation of the colon, and reactions to sedation.

How Long Does A Colonoscopy Procedure Take? 

The procedure will usually take anywhere from 30 to 60 minutes. Still, you should plan for more time to include preparation and recovery from sedation.